What the Anion Gap Measures
The anion gap is a practical way to understand acid-base balance by comparing the main measured electrolytes in blood with the ions that are not routinely measured. In practice, it guides clinicians evaluate whether an electrolyte imbalance is being driven by extra acids in the blood, a loss of bicarbonate, or another form of metabolic derangement.
On a basic chemistry panel, the main values used are sodium, chloride, and bicarbonate. The gap represents the difference between the positively charged ions and the negatively charged ions that are measured. Because the body contains many unmeasured anions and other unmeasured ions, the number is not expected to be zero. Instead, it provides a diagnostic clue that helps refine the etiology of metabolic acidosis.
In simple terms, the anion gap reflects the balance between measured cations and measured anions, plus the contribution of the body’s hidden acids. A rising gap suggests more acid is anion gap clinical significance present in the blood, often from organic acids or toxins. A normal gap, by contrast, often points toward bicarbonate loss with replacement by chloride, which creates a different pattern called hyperchloremic acidosis.
Think of the anion gap as a shortcut in the workup of acid-base problems: it does not give the full answer, but it quickly points toward the right differential diagnosis.
Because the measurement is tied to serum electrolytes and overall anion concentration, the result should always be interpreted alongside other laboratory values, including pH and bicarbonate on a blood gas.
How to Calculate the Anion Gap
The usual gap computation uses the main measurable ions on a serum chemistry panel. The classic formula is:
Anion gap = sodium - (chloride + bicarbonate)
The formula compares the dominant measured cation, sodium, against the main measured anions, chloride and bicarbonate. That difference reflects the amount of unmeasured anions in the blood.
An Anion Gap Calculator automates this math and minimizes errors when reviewing multiple sets of lab values. This is especially useful in fast-paced settings, where quick clinical interpretation is needed to support an acid-base analysis.
Example:
- Sodium: 140 Chloride: 102 Bicarbonate: 24
Using the formula, the anion gap is 140 - (102 + 24) = 14.
Reference ranges vary by laboratory, instrument, and whether potassium is included. Because of this, the most important step is to compare the result with the local normal range rather than relying on a single universal number. The calculator is a tool, but the interpretation depends on context, including whether the patient has systemic acidemia or a mixed disorder.
When using an Anion Gap Calculator, make sure the values come from the same sample and that the serum chemistry panel is clinically consistent with the blood gas. If chloride or bicarbonate is changing rapidly, a separate acid-base analysis may be needed to clarify the pattern.
Normal Anion Gap vs Increased Anion Gap Metabolic Acidosis
This acid-base disorder is a condition characterized by a fundamental reduction in bicarbonate, usually accompanied by a low pH on blood gas. The anion gap helps separate this into two major types: normal-gap metabolic acidosis and high-gap metabolic acidosis.
In high-gap metabolic acidosis, additional acids accumulate in the body. Those acids break apart and leave behind unmeasured anions, which widens the gap. This pattern is often a clue to lactic acid buildup, ketone production, kidney dysfunction, or toxin exposure.
In normal anion gap metabolic acidosis, bicarbonate is lost and chloride rises to preserve electrical neutrality. The gap stays within range, but the patient still has metabolic acidosis. This is why a normal number does not exclude serious disease.
The distinction matters because the acid-base disorder behind each pattern is different, and the etiologies, urgency, and next steps may differ as well. High-gap disorders usually point toward added acid, while normal-gap disorders usually point toward bicarbonate loss or impaired acid excretion.
A simple way to approach the result is:
- Establish acidosis with blood gas and pH. Review the anion gap on the serum chemistry panel. Assess whether the pattern is high gap or normal gap. Apply the pattern to guide the cause-focused workup.
This stepwise approach supports accurate clinical interpretation and helps identify the underlying metabolic derangement.
Common Causes of a Raised Anion Gap
Various disorders can cause high anion gap metabolic acidosis by adding acid to the bloodstream. The main idea is that the added acid generates unmeasured anions that increase the gap.
Lactic acidosis is one of the most common causes. It occurs when lactate builds up during poor oxygen delivery, shock, severe infection, seizures, or other states of increased metabolic demand. In this setting, the blood gas may show acidic pH, and the chemistry panel often reveals a widened gap.
Ketoacidosis is another important cause. It can occur in diabetes, prolonged fasting, heavy alcohol use, or starvation. Ketone bodies act as the excess acids, and their anionic forms increase the gap. In a patient with elevated glucose or a history suggestive of insulin deficiency, ketoacidosis becomes a leading consideration.
Renal failure can also cause a high gap because the kidneys are unable to clear organic acids normally. As kidney function declines, retained acids accumulate, creating a widening gap and contributing to systemic acidemia.
Toxic alcohols are critical not to miss. Ingestions such as methanol or ethylene glycol can cause severe high-gap acidosis. These toxins produce acidic metabolites and may also cause other striking clinical findings. In unexplained cases, toxic ingestion should remain on the differential diagnosis.
Other high-gap causes can include salicylate toxicity and certain inborn errors, but the most common practical categories remain lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The specific etiology often becomes clearer when the anion gap is interpreted with blood gas findings, glucose, ketones, kidney function, and clinical context.
Frequent Causes of a Regular Anion Gap
A normal anion gap metabolic acidosis typically indicates bicarbonate has been lost or chloride has risen to compensate. The result is a form of chloride-related acidosis, because the body retains electrical balance by raising chloride as bicarbonate falls.
Diarrhea is a classic cause. The gastrointestinal tract contains bicarbonate-rich fluid, and significant losses can lead to bicarbonate loss and metabolic acidosis. Because chloride rises to replace the missing bicarbonate, the anion gap often stays normal.
Tubular kidney acidosis is another important cause. In this group of disorders, the kidneys fail to excrete acid or conserve bicarbonate properly. The result is a normal-gap acidosis with acid accumulation or bicarbonate wasting, depending on the subtype.
Other situations can also lead to a normal gap, including certain medications, urinary losses, and iatrogenic chloride administration. However, the central pattern does not change: bicarbonate drops, chloride rises, and the gap does not increase much.
Recognizing this distinction helps avoid overcalling a high-gap process. A patient may still be quite ill with normal-gap acidosis, especially if the bicarbonate is low and the pH is clearly acidic. The goal is to identify the mechanism, not just the numeric category.
How to Correct the Anion Gap for Albumin
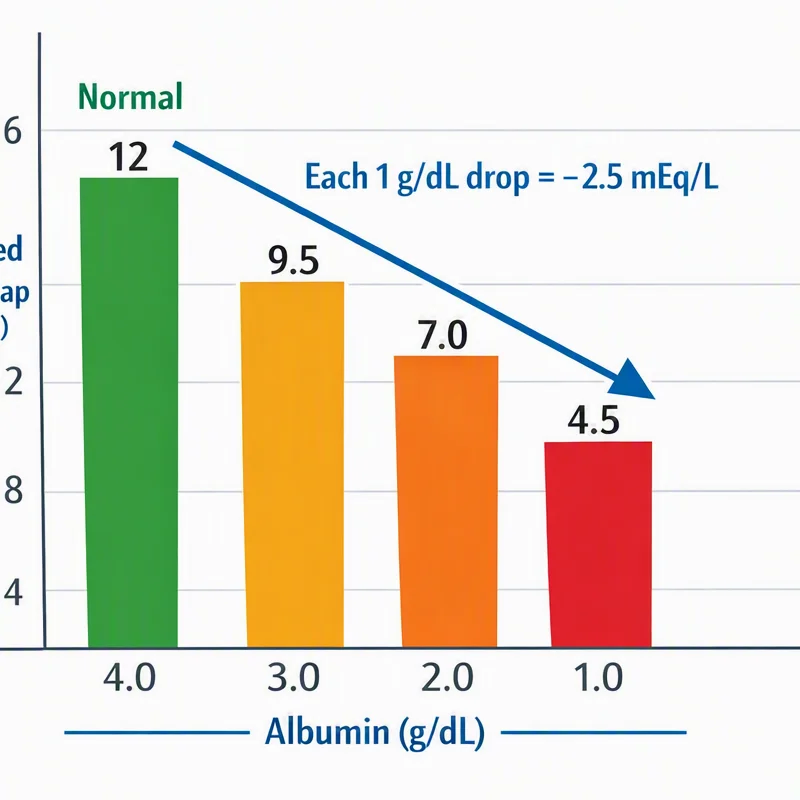
Albumin is a important negatively charged serum protein and an important contributor to the expected anion gap. Because it acts as an unmeasured anion, low albumin can make the measured gap appear apparently normal or only mildly elevated. That is why the corrected anion gap is often more informative than the raw value.
Hypoalbuminemia lowers the starting gap. If albumin is reduced, the body has fewer negatively charged proteins contributing to the measured difference, and the lab result may downplay the true burden of acids. This is especially critical in critically ill patients, where low albumin is common.
The general idea of albumin correction is to raise the anion gap upward when albumin is low. Different formulas exist, but the principle is the same: account for the missing negative charge so hidden acid accumulation is not overlooked.
Why this matters:
- A normal measured gap may mask a true high-gap disorder. The corrected value can more accurately show the real acid burden. Clinical decisions are more reliable when albumin is included in the interpretation.
In practice, the corrected anion gap is especially valuable when the serum chemistry panel and blood gas do not seem to match. If the pH suggests significant acidemia but the gap looks only mildly elevated, albumin correction can reveal a more meaningful abnormality.
How to Interpret the Anion Gap in Real Cases
Practical interpretation requires far more than remembering a formula. The anion gap should be evaluated alongside the blood gas, the serum chemistry panel, and the clinical picture. A patient with a low bicarbonate and acidic pH has true acidosis, but the cause depends on whether the gap is high or unchanged.
To begin with, establish the presence of acidemia on blood gas. A low pH indicates systemic acidemia, but the overall acid-base disorder may still be mixed. For example, a patient can have a primary metabolic acidosis plus respiratory compensation, or a mixed disorder that partly balances the pH.
Second, look at the gap and the albumin level. If albumin is low, calculate the corrected anion gap. A low albumin can hide a high-gap process, so the corrected value strengthens the clinical interpretation.
Finally, connect the result to the likely cause. Elevated lactate suggests lactic acidosis; ketones suggest ketoacidosis; kidney dysfunction points toward renal failure; and exposure history raises concern for toxic alcohols. A normal gap with low bicarbonate makes diarrhea or renal tubular acidosis more likely.
Take this practical example: a patient has low bicarbonate, an acidic pH, and an elevated gap on the chemistry panel. If albumin is also low, the corrected anion gap may be even higher, strengthening the suspicion for hidden acids. In another case, a patient with severe diarrhea may have low bicarbonate and high chloride but a normal gap, which fits hyperchloremic acidosis.
In short, the anion gap is a valuable diagnostic clue, but it works best when combined with the full laboratory picture rather than used alone.
When to Use an Anion Gap Calculator
An anion gap calculator is helpful any time you want a quick, reliable way to support diagnostic workup for suspected acid-base problems. It is especially useful when the lab values are changing or when multiple results need to be assessed quickly.
Use a calculator if:
- You are checking an electrolyte panel and worry about metabolic acidosis. You need to review serial serum electrolytes over time. You need fast acid-base analysis in a complex patient. You want to determine whether albumin may be masking a high-gap disorder. You are working through the differential diagnosis for an unexplained low bicarbonate.
For best results, the calculator should be used with the current measured sodium, chloride, and bicarbonate values from the same sample. When a patient has a major shift in volume status, kidney function, or treatment, the result should be checked again as part of ongoing clinical interpretation.
The calculator does not replace judgment. It supports the workup by translating raw numbers into a useful pattern, but the final answer still depends on the broader clinical context, including blood gas, history, exam, and other laboratory studies.
FAQs About the Anion Gap in Metabolic Acidosis
What is the anion gap in metabolic acidosis?
The anion gap is the difference between measured cations and measured anions, usually calculated from sodium, chloride, and bicarbonate. In metabolic acidosis, it helps show whether the acidosis is due to added acids, which raises the gap, or to bicarbonate loss with chloride replacement, which usually keeps the gap normal. It is a core tool in laboratory interpretation and acid-base analysis.
How do you calculate the anion gap from lab values?
Use formula: sodium - (chloride + bicarbonate). Those values usually come from the serum chemistry panel. An anion gap calculator can do this rapidly and reduce math errors. After the number is calculated, compare it with the lab’s reference range and interpret it with the blood gas and clinical context.
What indicates a high anion gap mean?
A high anion gap often means there are extra acids in the blood that create more unmeasured anions. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. It is an important clue in the assessment of high anion gap metabolic acidosis and should lead to a careful workup.
Why correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a primary unmeasured anion. If albumin is low, the measured gap may look less elevated than expected. A corrected anion gap helps reveal hidden acid accumulation, especially in patients with hypoalbuminemia or serious illness.
What leads to a normal anion gap metabolic acidosis?
Frequent causes include diarrhea, renal tubular acidosis, and other forms of AG vs OG interpretation bicarbonate loss. This pattern is often called hyperchloremic acidosis because chloride rises as bicarbonate falls. A normal gap does not mean the acidosis is minor; it just means the cause is usually different from that seen in high-gap disorders.