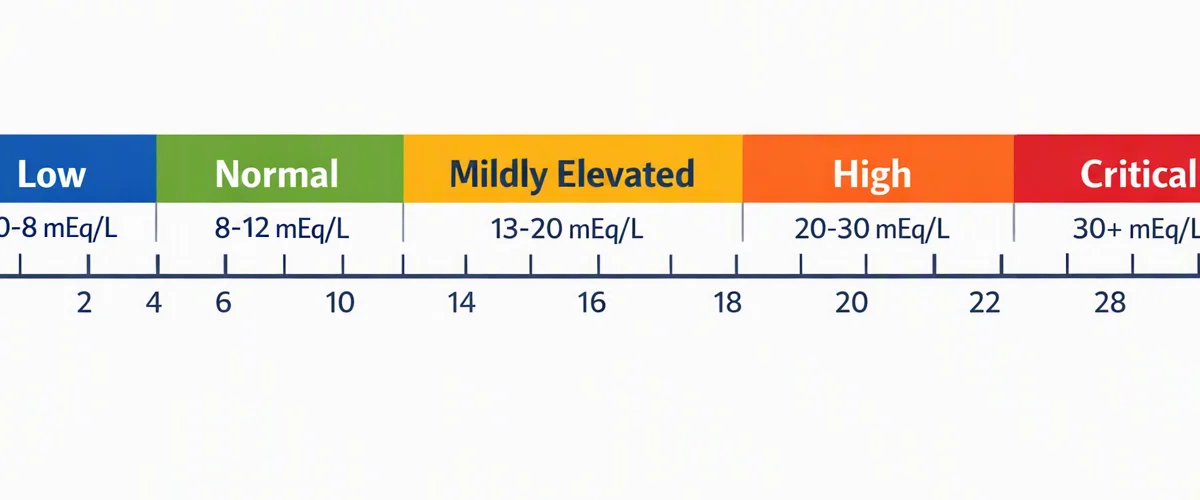
Understanding the Anion Gap?
The anion gap is a calculated value used to assist with interpreting an electrolyte panel. It examines the main measured cationic ions and negatively charged ions in the blood, especially sodium, chloride, and bicarbonate. Because routine testing does not measure every ion directly, the anion gap provides clinicians a useful snapshot of overall electrolyte imbalance and acid-base status.
In simple terms, the gap calculates the difference between unmeasured cations and unmeasured anions. A normal reference interval suggests that measured and unmeasured ions are fairly balanced. A low anion gap can signal a lab issue, a change in serum albumin, or the presence of abnormal proteins in the bloodstream. That is why careful lab interpretation matters. The Anion Gap Calculator helps carry out the gap calculation rapidly and consistently, making it easier to compare a test result against the expected range.
Although the anion gap is not a standalone diagnosis, it remains an essential screening test in routine chemistry. When it changes, clinicians often look at the broader pattern of the electrolyte panel rather than the number alone. That broader view is especially important when considering whether a result reflects true physiology or a laboratory artifact.
What Is Paraprotein excess?
Paraproteinemia describes the existence of an abnormal level of a single type of protein in the blood, usually a monoclonal protein or M-protein. This protein is generated by a clone of abnormal plasma cells. Since these cells come from one line of replication, they make one dominant type of immunoglobulins or immunoglobulin fragment rather than the broad mix normally seen in healthy immune function.
Paraproteinemia is a descriptive term, not a diagnosis by itself. It is often seen in monoclonal gammopathy, which includes conditions such as MGUS (monoclonal gammopathy of undetermined significance), multiple myeloma, and Waldenström macroglobulinemia. In these disorders, the abnormal protein may circulate at low or high levels and may act as a plasma protein with unusual electrical properties.
The same monoclonal pattern can appear as a monoclonal spike on testing. The clinical significance depends on the amount of paraprotein burden, the presence of symptoms, and whether there is evidence of organ involvement. A monoclonal protein can be benign, premalignant, or malignant, but any unexpected shift in protein chemistry deserves attention.
In What Way Paraproteins Alter the Anion Gap
Paraproteins can affect the anion gap because of their protein charge. Certain cationic proteins carry a net positive charge at physiologic pH. When these proteins increase, they can increase the amount of unmeasured cations in the blood. The result is often anion gap reduction, because the calculated gap shrinks as the chemistry panel tries to compensate for the ionic balance.
This effect is most notable when the abnormal protein behaves as a strongly charged paraprotein. In some cases, the charge characteristics of the monoclonal protein can push the chronic kidney disease AG elevation gap lower even before other abnormalities become obvious. That makes the anion gap a potential diagnostic clue in patients with subtle disease.
Hypoalbuminemia can amplify the effect. Albumin is one of the main negatively charged proteins in the blood, so lower albumin reduces the anion gap on its own. When low albumin and cationic paraproteins occur together, the measured number can fall further than expected. This is why the same low value may suggest more than one mechanism.
From a practical standpoint, the issue is not just whether the test result is low, but why it is low. A low value may represent true chemistry changes, a shift in protein balance, or a laboratory artifact. Distinguishing among these possibilities is the key to accurate interpretation.
How a Low Anion Gap Is Important
A decreased anion gap value is uncommon than an elevated one, so it should not be ignored. In many cases, the first step is to recheck the test and review whether the result fits the clinical picture. If the low value persists, it can point toward conditions such as paraprotein-related disorders, electrolyte errors, or drug effects.
One reason it matters is that it may be an early sign of diagnosis to a plasma cell disorder such as multiple myeloma. The finding does not confirm the disease, but it can raise suspicion when combined with anemia, bone pain, kidney dysfunction, or other abnormal labs. In the proper context, the anion gap becomes part of the overall argument for follow-up evaluation.
It is also important because a low value may be written off as meaningless if the clinician is not aware of charge effects. Yet a low result can reveal a hidden issue with proteins, especially if the patient has a known monoclonal gammopathy. That is why a careful review of the chemistry profile and protein studies is important.
A low anion gap is not a diagnosis, but it can be a important clue when viewed alongside protein studies, albumin, and the full electrolyte picture.
How to Understand Results with an Anion Gap Calculator
An Anion Gap Calculator helps standardize the analysis of the test result. It takes values from the electrolyte panel to compute the gap and match it with the expected reference range. This helps make it easier to notice when the result is abnormally low and may need further review.
Many calculators also support albumin correction, which is most useful when serum albumin is low. Because albumin reduces the anion gap when it decreases, an uncorrected result can minimize the true underlying gap. Correcting for albumin helps differentiate a low value caused by hypoalbuminemia from one caused by cationic paraproteins or another process.
For best interpretation, the calculator should be used with the full chemistry context: sodium, chloride, and bicarbonate, along with serum albumin and the patient’s clinical status. That combination improves lab interpretation and helps identify whether the test result reflects a normal variation, a laboratory artifact, or a important abnormality.
The calculator is especially helpful when trends matter. A single number may be less informative than repeated values showing persistent anion gap reduction. When the gap remains low across different draws and the albumin correction does not fully explain it, further evaluation becomes more important.
Frequent Reasons of a Reduced Anion Gap Besides Paraproteinemia
Paraproteinemia is just one likely cause of a decreased anion gap. In fact, more frequent causes should usually be considered first. One of the most common is hypoalbuminemia, since albumin is a primary hidden anion. When albumin drops, the gap can decline as well.
Other causes include drug or toxin effects. Lithium can lower the gap because it is an unmeasured cation. Bromide exposure can interfere with some lab methods and cause misleading chloride readings. Hypermagnesemia may also play a role by increasing hidden cations. In each of these situations, the issue is not the same as paraproteinemia, even though the final number may appear similar.
Laboratory artifact must continually remain on the list. A imperfect specimen, analytic interference, or unusual assay behavior can produce a spuriously low value. This is why a careful review of the entire electrolyte panel, repeated testing when appropriate, and comparison with earlier results are important parts of the workup.
Because the low anion gap has several causes, context matters. A low value in a person with normal albumin and no medication explanation may be more suggestive for a protein-related disorder than the same value in someone with obvious hypoalbuminemia.
When to Think About a Monoclonal Gammopathy
Monoclonal gammopathy should be suspected when a low anion gap continues without a different clear explanation, especially if there are further signs of protein abnormalities. This is particularly notable when the pattern points to a monoclonal protein rather than a nonspecific change in total protein. The presence of a low gap can be a subtle hint that abnormal plasma cells are producing excess immunoglobulins or related fragments.
The standard follow-up evaluation includes serum protein electrophoresis, which can reveal a monoclonal spike. Immunofixation helps identify the type of protein involved, while free light chains can uncover light-chain disease or quantify clonal activity more precisely. In some cases, beta-2 microglobulin is also informative because it can help assess disease burden and prognosis in plasma cell disorders.
These tests do not substitute for the anion gap; they follow it. The low gap acts as a marker that the chemistry profile may be leading toward a protein abnormality. When the signal is ongoing and reinforced by the rest of the clinical picture, the case for a monoclonal gammopathy becomes stronger.
It is also important to remember that not every paraproteinemia means cancer. MGUS may be unchanged and asymptomatic, while multiple myeloma and Waldenström macroglobulinemia require timely assessment. The role of the anion gap is to prompt the appropriate next step, not to determine the final diagnosis on its own.
FAQ
How can paraproteinemia reduce the anion gap?
Paraproteinemia can decrease the anion gap because certain monoclonal proteins behave like cationic proteins. Their positive charge increases unmeasured cations in the blood, which can lead to anion gap reduction. Stated differently, the gap narrows because the measured sodium, chloride, and bicarbonate values no longer reflect the full charge balance. The effect is stronger when the paraprotein has a larger protein charge contribution.
Is a low anion gap an early sign of multiple myeloma?
Yes, it can be an early diagnostic clue, but it is not specific for multiple myeloma. A low anion gap may show up before other findings become obvious, especially if there is a sizable monoclonal protein. However, it can also occur for other reasons, including hypoalbuminemia and laboratory artifact. This is why a low value should prompt review of the full clinical picture rather than be treated as a diagnosis by itself.
Is hypoalbuminemia a more common explanation for a low anion gap than paraproteinemia?
Yes, hypoalbuminemia is generally a more frequent cause of a low anion gap than paraproteinemia. Albumin is a major unmeasured anion, so when it falls, the gap usually drops as well. Still, paraproteinemia matters because it can create a low gap through a different mechanism, especially when monoclonal gammopathy or multiple myeloma is present. The best interpretation uses both the raw value and albumin correction.
Which tests should come after a low anion gap result?
If the low gap persists, common follow-up tests include a repeat electrolyte panel, serum albumin, and protein studies. The next steps often include serum protein electrophoresis, immunofixation, and free light chains. Depending on the context, clinicians may also check beta-2 microglobulin. These tests help determine whether the low anion gap reflects a paraprotein issue, a medication effect, or another cause.
Can an Anion Gap Calculator account for albumin changes?
Absolutely, an Anion Gap Calculator can be especially helpful when albumin correction is built in or used separately. This matters because albumin greatly affects the gap. Adjusting for serum albumin improves lab interpretation and helps show whether the low result is explained by hypoalbuminemia or whether it remains suspicious for a monoclonal protein effect. It makes the calculator a practical resource for reliable gap calculation and follow-up evaluation.