What’s the Anion Gap?
The anion gap is a derived value used to help interpret electrolytes in a blood chemistry panel. It offers clinicians and readers a quick way to evaluate acid-base balance by comparing the main measured positively charged and negative particles in the blood.
In practical terms, the anion gap can help estimate the amount of unmeasured anions in the bloodstream. It is not a direct lab measurement. Instead, it is a result calculation based on common serum electrolytes reported on an electrolyte panel, especially sodium, chloride, and bicarbonate.
This makes the anion gap a useful diagnostic aid when examining lab results and deciding whether an acid-base disorder may be present. A quick blood test interpretation can show whether the pattern is consistent with a normal anion gap, high anion gap, or low anion gap.
Anion Gap Formula in mmol/L
The basic formula for anion gap in mmol/L is straightforward:
Anion gap = sodium - (chloride + bicarbonate)
Some laboratories also report the values in mEq/L, but for typical clinical use, the numeric result is usually the same when the electrolytes are measured in usual millimole-based reporting. That is why many people can use an anion gap calculator without worrying too much about the unit label, as long as the lab values match the calculator’s expected format.
This equation uses the major measured ions:
- Sodium as the primary measured cation Chloride as a key measured anion Bicarbonate as another major measured anion
Because the calculation is based on measured ions, it helps identify variations in the balance of charged particles. For this reason the anion gap is often reviewed alongside other serum chemistry findings when evaluating acid-base balance.
How to Work Out Anion Gap In Steps
To calculate anion gap accurately, you need the specific serum sodium, serum chloride, and serum bicarbonate measurements from the same lab draw when available. Whether you use a calculator or doing the math by hand requires the same steps.
Here is a basic workflow:
- Find the serum sodium value. Find the serum chloride value. Locate the serum bicarbonate value. Sum chloride and bicarbonate together. Subtract that total from sodium.
For example:
If the serum sodium is 140 mmol/L, the serum chloride is 104 mmol/L, and the serum bicarbonate is 24 mmol/L, then:
Anion gap = 140 - (104 + 24)
Anion gap = 140 - 128 = 12 mmol/L
This calculation example shows why an anion gap calculator can be valuable: it minimizes arithmetic mistakes and offers quick clinical interpretation when reviewing electrolyte values.
Note: When comparing multiple lab panels, always verify that the same unit system is used and that the values come from the same blood chemistry panel.
Typical Anion Gap Range and Measurements
This normal range for anion gap varies by the laboratory’s reference interval and the way the test is displayed. In many settings, the typical reference range is approximately 8 to 12 mmol/L when potassium is not included, though some labs may use slightly different cutoffs.
Some labs present the result in mEq/L, and the number may appear nearly identical in routine use. Still, the best practice is to review the lab’s own reference interval rather than using only a generic range.
Why it matters:
- A value in the normal range does not always rule out an important issue. A result outside the expected reference range may indicate a true acid-base problem or a lab-related issue. Interpretation should always consider the full blood chemistry panel, not just a single value.
This wording anion gap in mmol/L is widely used in clinical discussions because it precisely matches many modern lab reports. Whether you see mmol/L or mEq/L, the key is to follow the lab’s own reference interval for reliable comparison.
What Does a Elevated Anion Gap Mean?
A increased anion gap commonly means that acid levels are higher in the blood, which can point toward acid-base imbalance. When this happens, the body has more unmeasured anions than expected, often due to the buildup of acid byproducts.
Typical causes of a high anion gap include:
- Lactic acidosis, in which lactate builds up because tissues are not using oxygen normally or because of other metabolic stress A ketoacid state, which can occur when ketone bodies rise significantly Other causes of acid-base disturbance that increase acid load
In clinical interpretation, the anion gap is just one indicator among several. A high result can support the idea of an acid-base problem, but it does not identify the exact cause by itself. This is why clinicians look at the full picture, including symptoms, glucose, kidney function, and other laboratory findings.
If you are using an anion gap calculator, a result above the lab’s normal range should prompt a careful review of the rest of the electrolyte panel and the patient’s context.
What Does a Low Anion Gap?
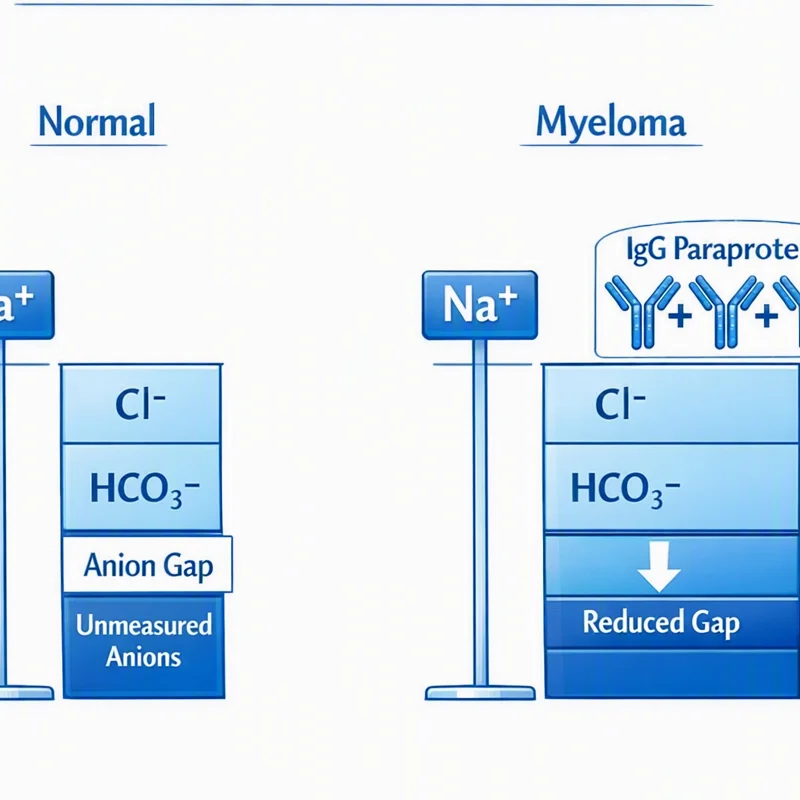
A decreased anion gap is less common than a elevated one, but it can still be significant. One of the leading explanations is hypoalbuminemia, because albumin is a negatively charged protein that helps maintain the relationship of measured and unmeasured ions.
Other possible reasons for a low anion gap include:
- Reduced albumin levels Laboratory error or testing issue More rarely, abnormal shifts in measured ions or proteins
Because laboratory error can sometimes produce an unexpectedly low result, it is often wise to run again the test or examine the raw values before drawing conclusions. A single abnormal number should not be interpreted in isolation.
In many cases, the first question is whether the result is truly low or whether it needs to be adjusted for albumin. That points directly to the idea of albumin correction.
How Serum Albumin Alters the Anion Gap
Albumin correction matters because serum albumin strongly affects the measured anion gap. Since albumin is a negatively charged protein, lower albumin often decreases the apparent calculated anion gap even when the underlying acid-base picture has not changed much.
For this reason clinicians often use a corrected anion gap. This can help make the result more useful when serum albumin is low, especially in patients with long-term illness, inflammation, or poor nutrition.
A typical approach toxic alcohol poisoning anion gap is to modify the anion gap upward when albumin is below normal. The specific correction formula can vary by institution, but the goal is the same: read the anion gap as if albumin were closer to a standard level.
Why this matters in practice:
- A low albumin level can make the anion gap appear normal when it is not or low. Corrected anion gap values can identify hidden metabolic acidosis. Albumin correction increases the accuracy of clinical interpretation.
When reviewing a result that seems inconsistent with the patient’s condition, checking serum albumin is often a practical next step. This is especially helpful when you are reviewing multiple lab results from the same blood chemistry panel.
When to Rely on an Anion Gap Calculator
An anion gap calculator is especially helpful when you want a quick and accurate result calculation from an electrolyte panel. It can reduce time and reduce manual math errors, especially when several values must be checked in a limited time.
You may want to use an anion gap calculator when:
- You are evaluating an electrolyte panel for signs of an acid-base disorder You need quick clinical interpretation of a blood chemistry panel You want to compare reference range values across different lab reports You are checking whether an abnormal result may represent metabolic acidosis
It is particularly useful when you need to compare serum electrolytes across repeated tests or when you want to understand the relationship between the numbers and the underlying physiology. A calculator is a practical diagnostic aid, but the final meaning still depends on the full clinical context.
Common Errors When Calculating Anion Gap
Even though the formula is simple, there are several common mistakes that can affect blood test interpretation. Paying attention to details can enhance the accuracy of the calculation and the reliability of the result.
- Units: Make sure you are using the right unit system and comparing results in the same format. Potassium: Some formulas include potassium, while others do not. Using the wrong version can change the result. Measurement error: A specimen problem or analyzer issue can distort the numbers. Reference values: Always compare the result to the lab’s specific reference values, not just a generic range.
Another common issue is mixing results from different time points. If sodium, chloride, and bicarbonate were not measured from the same sample, the anion gap formula may not reflect the patient’s true status. That is why the most dependable approach is to use the same serum chemistry set whenever possible.
Lastly, note that the anion gap is only one part of the larger clinical assessment. It should be considered alongside signs, repeat testing when needed, and other markers relevant to acid-base status.
Common Questions
How do you work out anion gap in mmol/L?
Apply the anion gap formula: sodium - (chloride + bicarbonate). Plug in the blood sodium, blood chloride, and bicarbonate level values from the lab report, then deduct the sum of chloride and bicarbonate from sodium. The final result is usually reported in mmol/L.
What’s the normal anion gap range in mmol/L?
The normal measurements depend on the lab’s reference span, but many labs use a typical range of about 8 to 12 mmol/L when potassium is not included. Always verify the specific lab report because the expected range can vary slightly.
Why is the albumin correction important for anion gap?
Correction for albumin matters because blood albumin is a major negatively charged protein. When albumin levels is low, the anion gap may appear falsely low or normal. A adjusted anion gap gives a more accurate view of the acid-base status and improves assessment.
What may a high anion gap indicate?
A elevated anion gap often points to metabolic acidosis caused by anion gap clinical significance extra acids or unmeasured anions in the blood. Common causes include lactic acid buildup and ketone-related acidosis. It is a helpful clue, but it should always be interpreted with the full clinical picture.
Should potassium be included in the anion gap formula?
That depends on the formula used by the lab or calculator. Some versions include K, while many common clinical calculations do not. If you use an anion gap calculator, check whether the tool includes potassium so the final calculation matches the intended method and reference values.