How the Anion Gap Measures
The anion gap is a measurement used to help interpret serum electrolytes and spot hidden acids in the blood. An anion gap calculator typically uses sodium, chloride, and bicarbonate to approximate the difference between measured positively charged and negatively charged ions. That difference can point to a metabolic derangement such as acid buildup.
At its core, the anion gap formula captures the balance of major ions on a standard electrolyte panel. When chloride and bicarbonate change in relation to sodium, the calculated gap alters. A higher-than-expected result suggests that unmeasured acids may be present in the bloodstream.
Because the anion gap is derived from routine blood chemistry, it is often used in the initial diagnostic workup of an acidotic state. It does not diagnose a disease by itself, but it helps narrow the underlying cause. In that way, it is a practical tool for clinical interpretation of acid-base disorders.
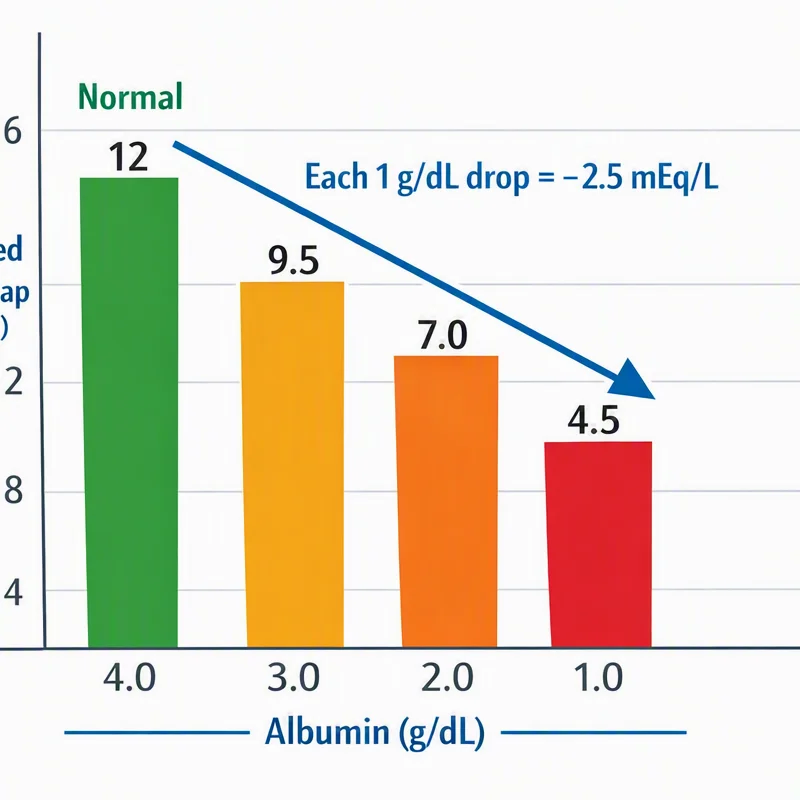
Normal values vary by laboratory, so the normal range depends on the assay and method used. Since albumin carries a negative charge, a low albumin level can make the measured gap appear smaller than it truly is. That is why clinicians often consider a corrected anion gap rather than relying on the raw number alone.
How Low oxygen Affects Acid-Base Balance
Hypoxia means too little oxygen at the tissue level, and tissue hypoxia can swiftly disrupt acid-base balance. When cells do not receive enough oxygen, they cannot rely on normal aerobic energy production. Instead, they shift toward anaerobic metabolism, particularly anaerobic glycolysis, which generates more lactate.
This shift is a form of oxygen deprivation response. The body tries to preserve energy production, but the tradeoff is acid accumulation. As lactate production rises, hydrogen ion burden also increases, pushing the body toward an acidotic pattern. That is why prolonged hypoxia can be linked to lactic acidosis.
The link between hypoxia and acid-base changes is not just about low oxygen in the blood. It often reflects cellular hypoperfusion, where oxygen delivery is impaired because blood flow is inadequate. In that setting, tissues become starved for oxygen even if the lungs are working to some degree. The result is a metabolic shift that can worsen a metabolic acidosis.
The body may mount a interpret low AG compensatory response, such as faster breathing, to reduce carbon dioxide and partially offset the acid load. Still, if the underlying problem continues, the metabolic disturbance can deepen. That is why hypoxia deserves attention whenever a patient has unexpected changes in blood gases or electrolytes.
Can Hypoxia Elevate the Anion Gap?
Indeed. Low oxygen can elevate the anion gap when it produces high anion gap metabolic acidosis, most commonly through lactic acidosis. When oxygen delivery is insufficient, cells switch to anaerobic energy pathways, and lactate builds up. Because lactate is an unmeasured anion, it elevates the gap calculated from the standard anion gap calculation.
That is why the answer is not simply “hypoxia raises the anion gap” in every case. It is more precise to say that oxygen deprivation can lead to elevated lactate, and elevated lactate can produce a high gap. The laboratory pattern depends on severity, duration, and the presence of other illnesses. A patient with mild low oxygen may not show major acid-base changes, while a patient with profound tissue hypoxia may develop clear metabolic acidosis.
In clinical practice, a rising anion gap often suggests that the body is accumulating acids faster than it can clear them. With hypoxia-related disease, the main acid is usually lactate. That makes lactate measurement essential when the anion gap calculator result seems abnormal and the patient has signs of poor perfusion or respiratory compromise.
A useful way to think about it: hypoxia does not directly “create” the gap, but it can trigger acid production that increases the gap.
So the relationship is indirect but important. Hypoxia leads to metabolic stress, metabolic stress leads to anaerobic metabolism, and anaerobic metabolism can lead to lactate accumulation. That chain is the physiology behind many cases of elevated gap acidosis in critical illness.
When Hypoxia May Not Raise the Anion Gap
Not all patient with hypoxia shows an elevated gap. Some people may have shifts in breathing without a large acid load. For example, respiratory alkalosis can occur in the early stages in hypoxemia because the person breathes faster and lowers carbon dioxide. In that case, the anion gap may stay normal even though oxygen levels are low.
Likewise, respiratory acidosis may happen when ventilation is poor, but that problem primarily increases carbon dioxide rather than producing a substantial load of unmeasured acids. The anion gap may stay within the expected normal range if there is no substantial metabolic component. These conditions show why blood gas results and electrolyte data must be reviewed together.
Someone may also have hypoxia with only slight or transient metabolic acidosis. If the episode is transient, lactate may not rise enough to alter the lab picture significantly. In other cases, the body clears lactate quickly once oxygen delivery improves. The result is a unremarkable or near-normal gap despite a clear hypoxic event.
This distinction matters because the anion gap is a marker of acid load, not oxygen level itself. You can have low oxygen without major acid accumulation. For that reason, an abnormal gap should prompt assessment for the actual metabolic cause, while a normal gap does not rule out significant hypoxia.
Additional Typical Causes of a Increased Anion Gap
Low oxygen levels is only one possible cause for increased anion gap values. Additional typical causes include ketoacidosis, renal failure, uremia, and toxic alcohols. Every of these issues creates unmeasured acids that raise the calculated gap.
Ketoacidosis happens when the body breaks down fat and produces ketones faster than they can be used or eliminated. That may be seen in diabetes, starvation, or alcohol-related illness. The result is a elevated-gap metabolic acidosis that can look like lactic acidosis on first glance.
Renal failure leads to impaired acid excretion, allowing organic acids and sulfate compounds to accumulate. In advanced kidney dysfunction, uremia becomes a key contributor to elevated gap acidosis. The kidneys cannot clear acids effectively, so the blood becomes progressively more acidotic.
Toxic alcohols such as methanol and ethylene glycol also cause dangerous acid-base disturbances. These substances are metabolized into acids that increase the anion gap. Because these cases can be life-threatening, a high gap should always be interpreted in the context of history, exposure risk, and the broader clinical picture.
How to Read an Anion Gap Calculator Result
When you use an anion gap calculator, begin by checking the input values for sodium, chloride, and bicarbonate. The reading offers a snapshot of the current electrolyte relationship, but the number alone is not enough. Meaning depends on albumin, the patient’s condition, and whether there is a mixed acid-base disorder.
When albumin is low, the measured gap may underestimate the true degree of acid accumulation. For this reason clinicians may apply a corrected anion gap. This adjustment helps avoid missing a significant metabolic disturbance in patients with malnutrition, liver disease, or prolonged hospitalization. In other words, albumin can mask clinically meaningful changes.
It is also essential to check bicarbonate. A low bicarbonate level supports the presence of metabolic acidosis, especially if the gap is elevated. However, bicarbonate alone does not reveal the cause. An elevated gap plus low bicarbonate suggests a process such as lactic acidosis, ketoacidosis, renal failure, or toxin exposure.
An arterial blood gas offers another layer of information. It helps determine pH, carbon dioxide, and compensatory patterns. In combination with the anion gap, it improves clinical interpretation and helps distinguish whether the issue is metabolic, respiratory, or mixed. This combined approach is more reliable than any single lab result.
Clinical Clues That Indicate Hypoxia-Driven Acidosis
Hypoxia-related acidosis is often considered when low oxygen saturation occurs alongside elevated blood lactate. A rising lactate level indicates that tissues are moving toward anaerobic metabolism because oxygen delivery is not enough. This is one of the most reliable clues that hypoxia is driving the metabolic picture.
Conditions such as sepsis and shock commonly cause this pattern. In sepsis, impaired circulation and cellular dysfunction can cause tissue hypoperfusion even before blood pressure falls sharply. In shock, oxygen delivery is markedly impaired, which can drive substantial lactate accumulation and a high anion gap.
Other signs may include rapid breathing, cool extremities, weak pulses, low urine output, or declining mental status. These findings point toward a systemic metabolic derangement rather than a mere isolated lab abnormality. The lab pattern becomes especially important when it matches the bedside picture of poor perfusion.
When these clues are present, the anion gap is best viewed as a marker of disease severity and metabolic stress. It does not replace clinical evaluation. Instead, it supports it by showing whether acid buildup has already become substantial enough to alter the blood chemistry.
When to Consider Urgent Medical Evaluation
Urgent evaluation is needed if hypoxia or a high anion gap occurs with confusion, shortness of breath, chest pain, or altered mental status. These symptoms can signal marked oxygen deprivation, major acid-base disturbance, or another life-threatening process. A delay in treatment can allow tissue injury to worsen.
A high anion gap plus breathing distress or poor circulation should be taken seriously. It may reflect severe lactic acidosis, sepsis, shock, or toxin exposure. In these situations, the right response is rapid medical assessment, oxygen support if needed, and a full diagnostic workup.
If the person is hard to wake, has labored breathing, or seems unable to think clearly, emergency evaluation is especially important. These features may indicate an acidotic state with inadequate oxygen delivery. Timely treatment can improve oxygenation and acid-base balance.
Frequently Asked Questions About Hypoxia and the Anion Gap
Can low oxygen cause a high anion gap?
Yes. Low oxygen can cause a high anion gap if it leads to tissue hypoxia and lactic acidosis. The primary reason is anaerobic metabolism, which increases lactate and creates a high anion gap metabolic acidosis. Not every case of low oxygen does this, but it is a classic pattern in severe illness.
Why does a lack of oxygen cause lactic acidosis?
When oxygen supply is insufficient, cells rely more on anaerobic glycolysis to make energy. That pathway produces more lactate than normal aerobic metabolism. As lactate increases, acid accumulation follows, producing lactic acidosis and potentially a higher anion gap.
Does every patient with hypoxia show an elevated anion gap?
No. A patient can have hypoxia without a high anion gap. Mild or short-lived oxygen deprivation may not cause enough lactate buildup to change the gap. Some patients may instead show respiratory alkalosis or a mixed pattern depending on the reason and severity of illness.
How does albumin influence the anion gap calculation?
Albumin is a key unmeasured anion, so decreased albumin can cause the measured gap look falsely low. This is why a corrected anion gap may be applied. Correcting for albumin helps uncover the true level of acid-base abnormality and improves clinical interpretation.
Which other conditions can increase the anion gap other than hypoxia?
Other important causes include ketoacidosis, renal failure, uremia, and toxic alcohols. These conditions also produce unmeasured acids, leading to metabolic acidosis. An anion gap calculator helps detect the pattern, but the underlying cause still requires specific evaluation.