What Is the Anion Gap?
The anion gap is a computed value from serum electrolytes that helps clinicians evaluate acid-base balance. It compares measured sodium with the measured anions chloride and bicarbonate to determine the amount of unmeasured anions in the blood. In routine blood chemistry, this gives the anion gap a helpful marker in a metabolic acidosis workup and a reliable part of patient assessment.
The basic idea is easy: the body maintains positive and negative charges in balance. When the gap is higher than expected, it can suggest excess acids or other unmeasured substances. That is why the anion gap is often applied as a diagnostic tool in the evaluation of metabolic acidosis and other acid-base disorder patterns.
The most common anion gap equation is:
Anion gap = Sodium - (Chloride + Bicarbonate)
This calculation relies on values from an electrolyte panel and gives a lab result that must always be interpreted in context. Because different laboratories may use slightly different measurement methods and normal values, the expected reference range can change.
How come Correct the Anion Gap for Albumin?
Albumin is the primary unmeasured anion in plasma, so it has a significant effect on the anion gap. When a patient has hypoalbuminemia, the original anion gap can look incorrectly normal or only mildly elevated even when clinically important acids are present. This is why the anion gap is often corrected for albumin.
Low albumin reduces the baseline gap because there are a smaller number of negatively charged proteins contributing to the measured balance. That can hide a significant metabolic acid load and reduce the sensitivity of the test for detecting metabolic acidosis. In other words, a patient with low albumin may have a “normal” gap on paper but still have an underlying high anion gap process.
Correcting the result enhances anion gap interpretation and supports stronger clinical significance. It helps distinguish true normal anion gap states from masked high-gap states in the setting of low albumin. This is especially important during critically ill patient assessment, where changes in albumin are common.
Corrected Anion Gap Formula and Working Steps
The adjusted anion gap refines the observed gap for the patient’s albumin concentration. The precise albumin correction factor may vary by guideline, but a typical approach is to add 2.5 mEq/L to the measured anion gap for every 1 g/dL albumin below 4.0 g/dL.
One common formula is:
Corrected anion gap = Measured gap + 2.5 × (4.0 - serum albumin in g/dL)
Example 1:
- Na = 140 Chloride = 104 Bicarbonate = 20 Serum albumin = 2.0 g/dL
First calculate the anion gap:
140 - (104 + 20) = 16
Then use the albumin correction:
2.5 × (4.0 - 2.0) = 5
Albumin-corrected anion gap = 16 + 5 = 21
This adjusted value suggests a increased burden of unmeasured anions than the unadjusted result might imply.
Illustration 2:
- Sodium = 138 Cl = 109 Bicarbonate = 24 Albumin = 1.8 g/dL
138 - (109 + 24) = 5
2.5 × (4.0 - 1.8) = 5.5
Adjusted anion gap = 10.5
While the uncorrected value is on the low side, the albumin-adjusted result stays within or near a typical reference range depending on the lab. This is why albumin correction matters so much in routine laboratory analysis.
To compute the anion gap correctly, follow these steps:
- Obtain sodium, chloride, and bicarbonate from the electrolyte panel. Calculate the measured anion gap using the anion gap equation. Assess the serum albumin level. Enter the albumin correction factor if albumin is low. Compare the corrected result with the lab’s reference range.
Note that some institutions use slightly different formulas or cutoffs, so the final interpretation should always account for the local reference range and method used by the medical calculator or laboratory system.
How to Work with an Anion Gap Calculator
An Anion Gap Calculator is a healthcare calculator that helps clinicians rapidly determine anion gap and provide albumin-adjusted interpretation. It is especially useful when reviewing a blood chemistry panel during a metabolic acid workup, because it minimizes arithmetic errors and speeds up decision-making.
To apply a calculation tool correctly, provide the relevant lab values exactly as reported:
- Sodium Chloride Bicarbonate Albumin
Some tools may require the serum bicarbonate directly, while others use total CO2 as a proxy depending on the lab format. Always make sure the values originate from the same electrolyte panel and represent the same sample to avoid inconsistency in the lab result.
When using an Anion Gap Calculator, the output usually shows:
- Measured anion gap Albumin-adjusted or corrected anion gap Reference range comparison
This supports clinical interpretation, especially when hypoalbuminemia is present. A calculator can also make it easier to compare repeated results over time and follow trends in acid-base disorder management.
That said, the calculation tool does not take the place of judgment. The calculator provides a number, but the clinician must decide whether the result fits the patient’s overall picture, including symptoms, medications, and other laboratory findings.
How to Interpret a Elevated or Normal Corrected Anion Gap
A high anion gap metabolic acidosis indicates that unnoticed acids are gathering in the blood. If the corrected value is above normal, the next step is to identify the source of the acid load. Common causes include lactic acidosis, ketoacidosis, renal dysfunction, and toxin exposure.
If the corrected anion gap is normal, the patient may have a normal anion gap pattern, often linked to bicarbonate loss or chloride gain rather than surplus unmeasured acids. This is commonly seen in some forms of diarrhea, renal tubular disorders, or saline-related acid-base changes. Even then, the overall clinical context remains essential.
Here is a practical way to think about the result:
- High corrected gap: consider high anion gap metabolic acidosis and look for unmeasured anions. Normal corrected gap: consider normal-gap processes and check chloride and bicarbonate shifts. Borderline result: review albumin, repeat testing if needed, and assess for mixed disorders.
In clinical practice, lactic acidosis may occur with shock, hypoperfusion, or severe illness, while ketoacidosis is often linked to diabetes, starvation, or alcohol use. Both can elevate acid production and increase the corrected gap. These patterns are a major part of anion gap interpretation because they inform urgent evaluation and treatment.
Frequent Causes of an Altered Corrected Anion Gap
An elevated corrected anion gap can reflect several important conditions. The differential diagnosis depends on whether the corrected value is high, unchanged, or unexpectedly low. In the context of a metabolic acidosis evaluation, the most important causes include renal failure, uremia, toxic alcohols, and salicylates.
Renal failure can increase the gap because the kidneys cannot remove acids normally, allowing metabolic acids to accumulate. As kidney function declines, retained acids contribute to uremic patterns and a higher gap.
Uremia is a well-known cause of high-gap acidosis due to retained organic acids and other unmeasured anions. In advanced kidney disease, this may be a major driver of abnormal blood chemistry values.
Toxic alcohols such as methanol or ethylene glycol can produce a dangerous high-gap state by creating acidic metabolites. When suspected, the clinical picture often includes neurologic changes, visual symptoms, or kidney injury, but the lab pattern may be the initial clue.
Salicylates can produce mixed acid-base patterns and may raise the anion gap through increased organic acids. The resulting picture can be multifaceted, so correlation with history and additional testing is essential.
Other causes of elevated corrected values may include:
- Lactic acidosis from poor perfusion or severe illness Ketoacidosis from diabetes, fasting, or alcohol-related states Toxin-induced metabolic acidosis Advanced renal dysfunction with acid retention
Understanding these trends improves diagnostic interpretation and supports appropriate next steps when the lab result is abnormal.
Restrictions, Pitfalls, and Medical Considerations
The adjusted anion gap is helpful, but it is imperfect. One major issue is lab error. Small inaccuracies in sodium, chloride, or bicarbonate can meaningfully change the final result, especially when the gap is only modestly abnormal. Rechecking values may be appropriate when the pattern does not fit the clinical picture.
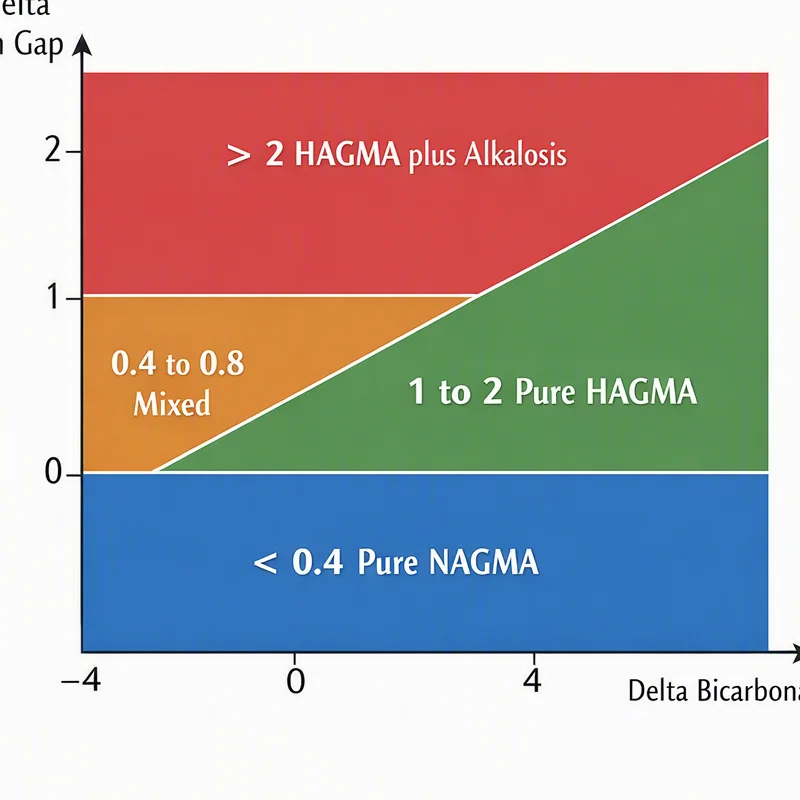
Another key concept is the delta gap, which compares against the rise in the anion gap with the fall in bicarbonate. This can help identify mixed acid-base disorders. For instance, Additional resources a high gap with a lower-than-expected bicarbonate drop may suggest an additional metabolic alkalosis, while the reverse can suggest a coexisting non-gap process.
Mixed acid-base disorders are often seen in sick patients, and the corrected anion gap should be used as part of a wider clinical interpretation rather than as a single answer. The result should be considered alongside pH, pCO2, lactate, ketones, kidney function, and medication history.
Additional pitfalls include:
- Relying on outdated or mismatched lab values from different collection times Ignoring albumin when it is clearly low Applying the wrong correction factor for the lab method Failing to notice a normal anion gap process masked by other abnormalities
Good clinical interpretation requires the full picture. The corrected anion gap is a guide, not a diagnosis. It should support the broader assessment of the patient, especially when symptoms, blood gas data, and biochemical markers point in varying directions.
Frequently Asked Questions: Adjusted Anion Gap Questions
How is calculated corrected anion gap?
First determine the anion gap using sodium minus the sum of chloride and bicarbonate. After that adjust it for albumin using an albumin correction factor, commonly 2.5 mEq/L for each 1 g/dL that albumin is below 4.0 g/dL. This gives an albumin-adjusted result that is more accurate in patients with low albumin.
What is the value of the albumin correction factor for anion gap?
A commonly used albumin correction factor is 2.5 mEq/L per 1 g/dL decrease in albumin below 4.0 g/dL. Certain references or references may use slightly different values, so the exact method should match the reference range and the calculation tool being used.
How does low albumin lower the anion gap?
Albumin is a major unmeasured anion in blood. With low albumin, fewer negative charges are present, so the measured anion gap decreases. This can cause a high-gap disorder appear less obvious unless the result is corrected for albumin.
What does a high corrected anion gap mean?
A high corrected anion gap usually means there are excess unmeasured acids in the blood. Common causes include high anion gap metabolic acidosis from lactic acidosis, ketoacidosis, renal failure, uremia, toxic alcohols, or salicylates. It is a clue that further diagnostic interpretation is needed.
When is it appropriate for an anion gap calculator be used?
An Anion Gap Calculator should be used whenever you need to calculate anion gap quickly and accurately, especially if albumin is low or the acid-base disorder is not straightforward. It is especially helpful during metabolic acidosis workup, routine electrolyte panel review, and any situation where corrected interpretation may change the clinical significance of the lab result.