What Is the Anion Gap?
The anion gap is a computed value used to help interpret serum electrolytes and identify possible problems in acid-base balance. It represents the difference between the main measured positively charged particles and negative ions in the blood. In practical terms, it assists clinicians and patients determine whether an unexpected acid is present in the body.
The calculation is based mainly on sodium, chloride, and serum bicarbonate, which are part of a standard serum electrolyte panel. These values come from common blood chemistry or serum chemistry testing. Because unmeasured ions also contribute to the total, the result is an indirect estimate of anion concentration rather than a direct measurement.
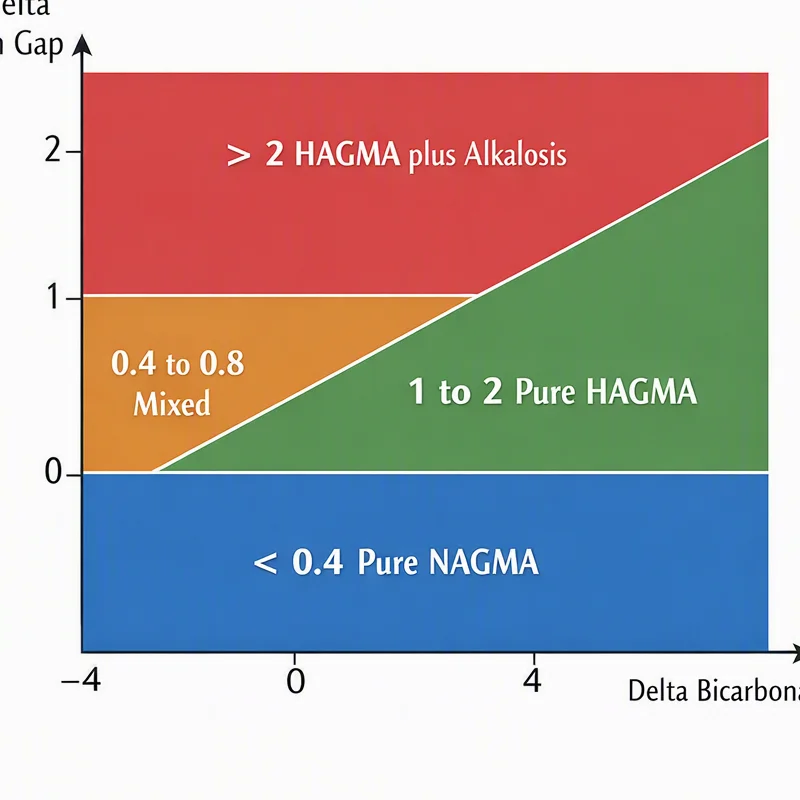
An elevated or reduced gap can point toward an acid-base disorder, especially metabolic acidosis. That makes the anion gap a useful diagnostic aid in laboratory interpretation and clinical assessment. It is not a standalone diagnosis, but it can quickly guide further evaluation.
In What Way the Anion Gap Calculator Functions
An anion gap calculator employs a basic formula using routine laboratory values. The standard version is:
Anion gap = Sodium − (Chloride + Bicarbonate)
Certain versions also add potassium in the formula:
Anion gap = Sodium + Potassium − (Chloride + Bicarbonate)
As potassium is usually present in a reduced concentration than sodium, many clinicians prefer the first version for everyday use. Even so, the choice of formula depends on the method used by the laboratory and the mode of result interpretation being applied.
This electrolyte formula is part of a broader method to electrolyte analysis. It helps clinicians calculate anion gap values in the setting of suspected acid-base problems, especially when checking a serum electrolyte panel alongside the patient’s symptoms and other test results.
When the gap is elevated than expected, it can suggest that unmeasured acids are accumulating. When it is lower than expected, it may indicate changes in albumin, abnormal proteins, or a measurement issue. In both cases, the number must be evaluated in context, not in isolation.
How to Operate the Internet Calculator
Working with online tool is simple. Type in the available input values from your laboratory results, including serum sodium, serum chloride, and serum bicarbonate. If the calculator includes a potassium option, you may also enter potassium when instructed.
Before getting started, make sure the numbers come from the same what high AG indicates sample and are reported in the same unit system. Minor variations in collection timing or reporting methods can affect the outcome. A good medical calculator should allow quick entry while still supporting accurate electrolyte analysis.
After adding the serum sodium and serum chloride values, the calculator performs the subtraction automatically and displays the estimated anion gap. Some tools may also offer an albumin correction option if serum albumin is available. That adjustment can support result interpretation when protein levels are abnormal.
For best use, think of the calculator as a efficient way to arrange data from a serum electrolyte panel. It does not replace medical judgment, but it can support a careful review of the patient’s laboratory interpretation and possible electrolyte imbalance.
Typical Anion Gap Range & Explanation
The normal range for the anion gap depends on the laboratory method, the formula used, and the sampling site. For that reason, each result should be compared with the lab-specific reference range. A value that is normal in one lab may be somewhat different in another.
In general, the anion gap is used as part of metabolic acidosis evaluation. A higher-than-expected value often points to a elevated anion gap state, while a reduced value may point to a low anion gap. Both can be medically important, but the meaning depends on the complete context of the patient’s acid-base status.
Clinicians often review the number alongside pH, bicarbonate, and other electrolytes to determine whether there is an acid-base imbalance. A normal gap does not exclude illness, and an abnormal gap does not identify the exact cause on its own. It simply limits the possibilities and helps with medical assessment.
One important point is that a normal result does not always rule out all forms of acidosis. Some patients have a hyperchloremic acidosis, which means bicarbonate is low but the gap is not elevated. That pattern requires a different interpretation than elevated gap acidosis.
High Anion Gap Causes
A increased anion gap typically means there are additional acids in the blood that are not routinely detected by standard electrolytes. This pattern is central to metabolic acidosis workup and should prompt review of the patient’s symptoms, medical history, and additional labs.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. Each of these conditions raises unmeasured acid in the bloodstream, which raises the calculated gap.
- Lactic acidosis can occur when the body generates too much lactate or cannot clear it properly. Ketoacidosis is commonly associated with uncontrolled diabetes, starvation, or heavy alcohol use. Renal failure can impair the body’s ability to clear acids effectively. Toxic alcohols, such as certain ingested solvents, can produce marked metabolic disturbance.
These causes are not all-inclusive, but they represent the most frequently cited categories in laboratory interpretation. A elevated result should be treated as a signal to look deeper rather than a final diagnosis. The calculator helps highlight the abnormality, but the underlying cause still requires targeted evaluation.
Decreased Anion Gap Causes
A low anion gap is uncommon, but it can be just as important. One of the most frequent explanations is hypoalbuminemia, because albumin is a major unmeasured negatively charged protein in the blood. When albumin falls, the calculated gap may also drop.
Other possible causes are multiple myeloma, where abnormal proteins can affect the gap, and lab error, which should always be carefully be considered when a result seems unusual. Certain electrolyte changes, including hypercalcemia, may also contribute to a reduced value in some situations.
When a low result appears, the first step is often to verify the measurement and confirm there is no lab error. Then clinicians review total protein, albumin, and the broader picture of electrolyte imbalance. A low gap is not always dangerous, but it should not be overlooked if the value is persistently abnormal.
Because low values can indicate changes in protein or measurement rather than acid production, they require thoughtful interpretation. The calculator can identify the pattern, but only a clinician can determine whether the finding is meaningful in the current clinical setting.
Albumin Correction and Patient Context
Albumin correction is essential because serum albumin has a major effect on the anion gap. When albumin is low, the calculated number may underestimate the true level of unmeasured acids. Correcting for albumin can therefore provide a more accurate albumin-corrected anion gap.
This adjustment is especially useful when evaluating a patient with suspected metabolic acidosis or when looking for hidden abnormalities in nutritional status. A person with low albumin may appear to have a near-normal gap even when significant acid accumulation is present. In that case, failing to account for albumin could cause a missed clue during patient evaluation.
Albumin correction does not replace the original calculation. Instead, it offers context. A clinician may review both the raw and corrected values to understand whether a low albumin level is masking a increased anion gap. This is one reason the anion gap is best used as part of a larger diagnostic review rather than as a single-number answer.
When anion gap clinical significance available, albumin should be interpreted alongside the rest of the serum electrolyte panel. That broader view helps connect the calculator output to the patient’s actual physiology and improves result interpretation.
Constraints of the Calculator
This online tool is a practical screening tool, but it has several limitations. It depends on correct entry of data, standardized lab methods, and proper clinical context. Even small differences in laboratory variability can alter the apparent result.
The tool cannot provide a clinical diagnosis by itself. It can show whether the gap is greater than or under the expected reference range, but it cannot determine the full cause of the abnormality. That requires review of symptoms, history, medications, other tests, and the overall electrolyte imbalance.
Another limitation is that the calculator does not account for each factor that affects acid-base status. Different laboratories may use slightly different methods, and the same patient may yield different numbers under different conditions. This is why any abnormal value should be checked against the broader picture of acid-base balance and not treated as a standalone answer.
Used correctly, the calculator is a efficient diagnostic aid for fast review, but it is still only one part of a larger clinical assessment. It helps thinking; it does not replace it.
Frequently Asked Questions About Anion Gap Calculation
What does an anion gap calculator used for?
An anion gap calculator is used to rapidly estimate the anion gap from basic laboratory values such as serum sodium, serum chloride, and serum bicarbonate. It helps with laboratory interpretation, especially when evaluating metabolic acidosis and other acid-base disorder patterns. It is a useful medical calculator for reviewing a serum electrolyte panel and guiding further assessment.
What is a normal anion gap range?
The normal range depends on the lab’s method and the formula being used, so the best comparison is the local reference range. In general, the result should be interpreted in the context of the specific lab report. A value outside the expected range may suggest a high anion gap or low anion gap, but the meaning depends on the rest of the clinical picture.
What can cause a high anion gap?
Common causes of a high anion gap include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These issues elevate unmeasured acids in the blood and can indicate a serious metabolic acidosis. A high result should always be followed by more thorough clinical assessment rather than used as a final diagnosis.
Why does albumin correction important in anion gap calculation?
Albumin correction plays a role because low serum albumin can lower the measured gap and mask a true abnormality. Applying a corrected anion gap helps adjust for changes in protein status and can reveal a more accurate estimate of unmeasured acids. This is especially useful when reviewing suspected high gap acidosis.
Can a calculator diagnose the cause of an abnormal anion gap?
No. The calculator is a helpful screening tool and diagnostic aid, but it cannot diagnose the cause on its own. It can reveal whether there is an abnormal result, but the underlying cause still requires medical evaluation, review of electrolytes, and consideration of other findings. Conditions such as hypoalbuminemia, multiple myeloma, lab error, and broader electrolyte imbalance must all be interpreted in context.