What exactly is the Anion Gap?
The anion gap is a derived value calculated from common electrolytes in a blood test. It assists clinicians evaluate acid-base balance and identify potential sources of unmeasured anions in the blood. In practice, the anion gap is a helpful diagnostic aid when reviewing serum chemistry results during a clinical assessment.
Most often, the calculation uses sodium and chloride, along with bicarbonate. Because these lab values reflect the balance of charged particles in the bloodstream, the anion gap can point to an underlying metabolic disorder such as metabolic acidosis. A blood test may look otherwise routine, but the anion gap can highlight important clues about an electrolyte imbalance.
Although the name suggests a gap, it is not a true empty space. Instead, it is an estimate of the difference between measured cations and measured anions. That makes it an key concept in clinical interpretation of lab results and a standard part of the metabolic acidosis workup.
Anion Gap Equation and Calculator Inputs
The formula for the anion gap is usually based on 3 main laboratory values: Na, Cl, and HCO3. Many clinicians use an Anion Gap Calculator to speed up the math and reduce manual errors when checking a lab result.
The standard formula is:
Anion gap = serum sodium − (serum chloride + serum bicarbonate)
Certain versions of the calculation also include potassium. If potassium is included, the equation becomes:
Anion gap = (serum sodium + potassium) − (serum chloride + serum bicarbonate)
Both methods are used in clinical practice, but the potassium-inclusive version is less common because potassium usually contributes only a limited amount to the final value. The most important thing is to know which method your laboratory or clinician uses so the interpretation stays uniform.
An anion gap calculator is especially useful when comparing serial results, tracking subtle shifts in lab values, or checking whether an elevated result may indicate a true acid-base problem. It offers a fast estimate of the anion gap using standard blood test inputs and can support broader medical interpretation.
How to Work out the Anion Gap Step-by-Step
To determine the anion gap on your own, you need three key measurements: serum sodium, serum chloride, and serum bicarbonate. The process is easy to follow and can be used to check a calculator result.
Follow these steps:
- Begin with the serum sodium value. Include serum chloride and serum bicarbonate together. Deduct that total from the sodium value.
Here is a clear calculation example:
- Serum sodium = 140 Serum chloride = 102 Serum bicarbonate = 24
Now use the formula:
140 − (102 + 24) = 140 − 126 = 14
In this example, the anion gap is 14. Based on the lab’s reference range, this may be typical or only mildly elevated. A single number should always be interpreted alongside the full clinical picture, including symptoms, the broader serum chemistry panel, and other markers of acid-base status.
Some clinicians also review whether the result suggests a likely metabolic acidosis, especially if the bicarbonate is low. In that scenario, the anion gap can guide the next steps in the differential diagnosis.
Normal Anion Gap Range and Reference Values
The normal range for the anion gap can vary depending on the laboratory, the analyzer, and whether potassium is included. That is why the reported reference interval matters more than any one universal cutoff.
Overall, many labs use a reference interval that falls somewhere around the low teens, but the exact number depends on the method and local laboratory variation. Because of this variation, two people with the same lab values may receive slightly different interpretations depending on where the blood test was processed.
Albumin also affects the expected value. Since albumin is a major negatively charged protein in the blood, lower albumin can reduce the measured anion gap even when the underlying acid-base picture is abnormal. That is why the normal range must be https://anion-gap-chart250.wordcanopy.com/posts/how-hyperalbuminemia-affects-the-anion-gap considered in context rather than treated as a fixed universal value.
When reviewing a lab result, it is best to compare it with the specific reference range printed by the laboratory. This helps ensure that the reading reflects the correct assay and avoids overcalling a result as abnormal.
What High and Reduced Anion Gap Results Indicate
A increased anion gap often suggests higher levels of acidic substances in the blood. This pattern is especially important in metabolic acidosis, where bicarbonate is consumed as the body buffers acid. In that context, the elevated gap hints at a problem beyond simple bicarbonate loss.
A low anion gap is less common, but it can nevertheless be clinically meaningful. One frequent cause is hypoalbuminemia, because albumin helps form the normal unmeasured anion pool. Other causes may include testing problems or abnormal proteins in the blood.
Either high or low values should be interpreted as part of a larger clinical assessment. A single lab value rarely provides the full answer. Instead, the anion gap acts as a signal that helps refine the differential diagnosis and guide a more targeted evaluation of the patient’s acid-base status.
Reasons of High Anion Gap Metabolic Acidosis
Whenever the anion gap is increased, clinicians often consider causes of high anion gap metabolic acidosis. This process increase the amount of unmeasured acids in the bloodstream and shift the balance of electrolytes.
Common causes include:
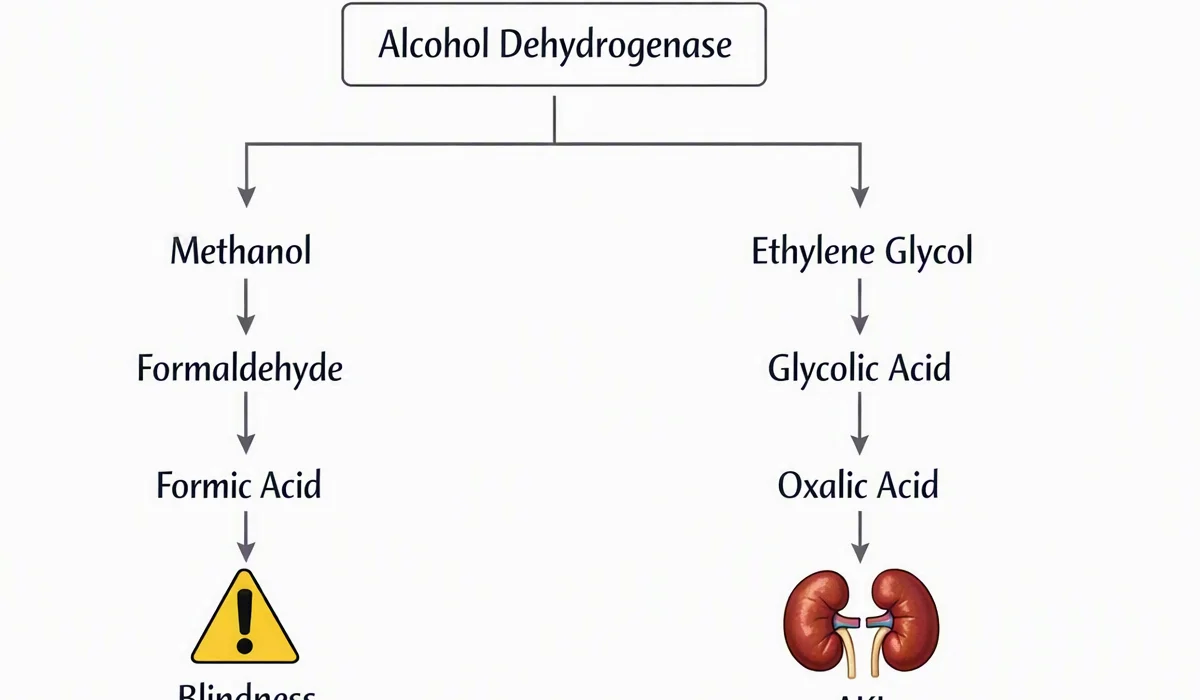
- Lactic acid buildup, where lactate accumulates during tissue hypoxia, shock, seizure, or severe illness. Ketone acidosis, which can occur in diabetes, starvation, or heavy alcohol use. Kidney failure, when the kidneys cannot clear acids effectively. Alcohol toxins, such as methanol or ethylene glycol, which create dangerous acid metabolites.
Such findings matter because they can signal a serious metabolic disorder requiring urgent treatment. In a metabolic acidosis workup, the anion gap helps separate between acid loss and acid accumulation. A higher gap often implies that the body is dealing with added acids rather than simply losing bicarbonate.
Clinicians may also use the anion gap as part of a broader differential diagnosis. For example, in someone with altered mental status and an unexplained acid-base disorder, the result may help prioritize toxic ingestion, renal impairment, or severe infection.
Causes of Low Anion Gap
A low anion gap can arise for several reasons, and it should not be dismissed. The main explanation is hypoalbuminemia, since less albumin means fewer negatively charged proteins in circulation. This alters the measured balance and can lower the calculated result.
Other additional causes include:
- Hyperalbuminemia, though this is less often a genuine clinical issue than a testing-related or level-related finding. Multiple myeloma, where abnormal proteins can alter the serum charge balance. Paraproteins, which may act as positively charged proteins and lower the calculated gap. Lab error, including specimen or measurement problems that affect the result.
Because a low result can sometimes suggest a testing issue rather than a disease process, it is wise to review the sample quality and repeat the test if needed. In clinical practice, a low anion gap may be the first clue to an abnormal protein state or an electrolyte pattern that deserves more thorough evaluation.
Correcting the Anion Gap for Albumin
Albumin correction is an important step when interpreting the anion gap, especially anion gap clinical significance if serum albumin is low. Since albumin contributes substantially to the normal anion gap, a reduced albumin level can make the measured value appear falsely low.
The goal of a albumin-corrected anion gap is to approximate what the result would be if albumin were normal. This offers a more accurate view of the underlying charge balance in the blood and improves anion gap estimation in patients with protein-related changes.
Various formulas may be applied, but the general principle is the same: make a correction factor based on the albumin level. When albumin is low, the corrected number may reveal a hidden high anion gap that was masked by the reduced protein concentration.
This step is especially useful in patients with serious illness, malnutrition, chronic disease, or inflammation, where albumin is often below normal. Without albumin correction, clinicians may misjudge the severity of an acid-base disturbance and fail to recognize an important part of the diagnosis.
How Clinicians Use the Anion Gap in Acid-Base Interpretation
The anion gap is one piece of a larger acid-base puzzle. Clinicians use it to help classify acid-base disorders, investigate suspected metabolic acidosis, and interpret the result with other laboratory findings. It is infrequently used alone.
For example, if a patient has low bicarbonate and a high anion gap, that pattern supports an acid buildup process such as lactic acidosis, ketoacidosis, renal failure, or toxic alcohol ingestion. If bicarbonate is low but the gap is normal, the cause may be a different issue altogether, such as gastrointestinal bicarbonate loss or renal tubular problems.
The anion gap is also helpful when reviewing metabolic alkalosis or respiratory disorders. In those settings, clinicians look at the entire pattern of pH, carbon dioxide, bicarbonate, and electrolytes to understand whether the body is compensating appropriately. The anion gap may provide extra context even when it is not the main abnormality.
One more valuable principle is the delta gap, which evaluates the shift in the anion gap with the shift in bicarbonate. This helps detect combined acid-base disturbances and can indicate whether more than one process is occurring at the same time. In complicated cases, the delta gap adds depth to the clinical interpretation and enhances diagnostic accuracy.
In general, the anion gap supports acid-base balance evaluation by turning routine lab values into actionable insight. It is a useful tool for interpreting a blood test, structuring the workup, and clarifying the clinical significance of electrolyte shifts.
Frequently Asked Questions About the Anion Gap Calculator
What is the anion gap calculator used for?
The anion gap calculator is used to estimate the anion gap from routine lab values and aid clinical interpretation of acid-base status. It helps identify possible causes of metabolic acidosis, assess electrolyte imbalance, and direct the differential diagnosis when a blood test shows abnormal serum chemistry results.
How do you calculate the anion gap formula?
The standard anion gap formula is serum sodium − (serum chloride + serum bicarbonate). Some versions also add potassium, but the sodium-based formula is the most common. An online calculator or manual calculation can both give the result, as long as the same lab values are used consistently.
What is a normal anion gap range?
The normal anion gap depends on the laboratory’s reference range and the analyzer used. Because of laboratory variation, the exact normal range can change from one lab to another. Albumin level also affects the expected result, so the reference interval should always be reviewed alongside the lab report.
Why is the anion gap high in metabolic acidosis?
The anion gap is high in metabolic acidosis when unmeasured acids accumulate in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. These conditions raise unmeasured anions and lower bicarbonate, producing a higher calculated gap.
Should the anion gap be corrected for albumin?
Absolutely, adjustment for albumin can be helpful when albumin in the blood is low. Since albumin plays a role in the normal anion gap, hypoalbuminemia can conceal a true elevation. A adjusted anion gap provides a more accurate view of electrical balance and can aid interpretation in challenging cases.