What an anion gap calculator measures
An anion gap calculator is a useful diagnostic tool used during clinical assessment of acid-base disorders. It determines the anion gap from routine serum measurements, most commonly serum sodium, serum chloride, and serum bicarbonate. This result helps clinicians identify an acid-base imbalance and decide whether the pattern suggests a hidden acid load, impaired acid clearance, or another form of metabolic derangement.
In basic form, the calculator compares measured cations and anions in the electrolyte panel. A widened gap often signals unmeasured acids in the blood, which is why the tool is so valuable in lab interpretation. It does not diagnose a single condition by itself, but it helps narrow the differential diagnosis when a patient presents with poisoning, shock, renal dysfunction, or unexplained neurologic findings.
For suspected poisoning, the anion gap calculator is especially important because it can reveal a high anion gap metabolic acidosis even before the full clinical picture is obvious. In isoniazid toxicity, this can support urgent recognition of serious systemic toxicity and prompt quicker treatment decisions.
The reason anion gap matters in isoniazid toxicity
Isoniazid toxicity and isoniazid overdose can be critical emergencies because they can produce profound metabolic acidosis, lactic acidosis, and nerve-related symptoms such as seizures. The anion gap matters because it indicates the accumulation of acids that are not directly measured by the standard electrolyte panel. In toxin exposure, this often becomes one of the earliest clues that a poisoning syndrome is present.
Isoniazid can disrupt pyridoxine-dependent pathways, lowering gamma-aminobutyric acid activity and triggering neurologic toxicity with refractory seizures. Seizure activity increases lactate production, and the resulting lactic acidosis can drive the anion gap higher. So, while the elevated gap is not specific to isoniazid, it aligns with the overall pattern of severe poisoning and helps reinforce the need for urgent treatment.
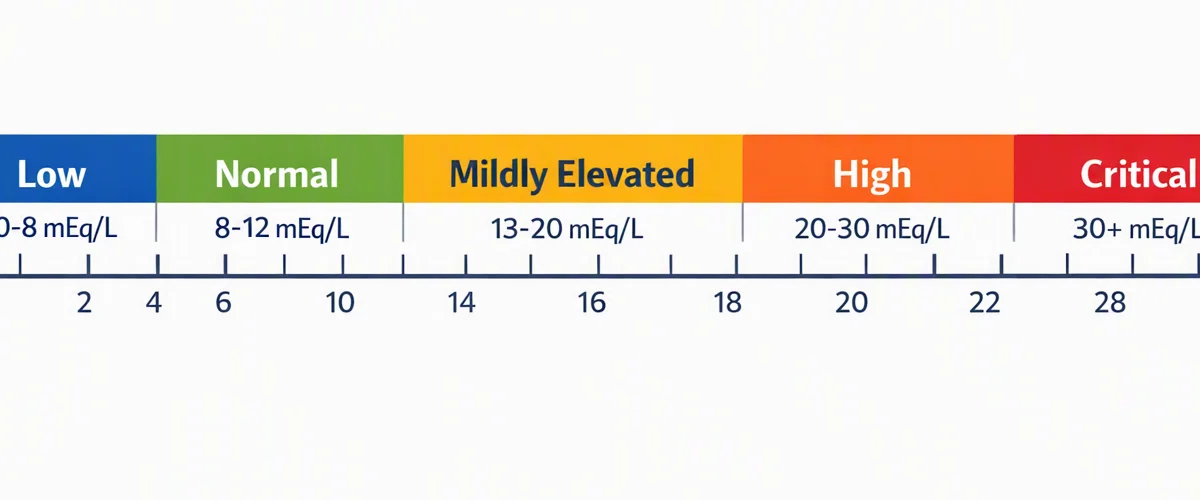
In practical terms, a markedly elevated gap in a patient with overdose symptoms, altered mental status, and seizures should prompt concern for a toxicologic cause. The anion gap calculator becomes part of the emergency management workflow: it aids recognition of the metabolic abnormality, helps guide additional testing, and keeps the team focused on antidotal therapy and seizure control.
How to find the anion gap
The usual anion gap formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
This method uses routine serum measurements and is https://anion-gap-reader007.quillnesty.com/posts/how-to-use-an-anion-gap-calculator-for-lab-tests easy to apply at the bedside or through an anion gap calculator. This value estimates the amount of unmeasured anions in the blood. A normal result suggests that bicarbonate loss or other non-gap processes may be present, while an elevated result suggests retained acids or toxin-related metabolic acid accumulation.
It is essential to distinguish a normal anion gap from a high anion gap pattern. A normal gap does not rule out serious illness, but it changes the differential diagnosis. A high gap points toward conditions such as lactic acidosis, ketoacidosis, renal failure, or poisoning. In isoniazid poisoning, a high gap usually reflects a combination of seizure-related lactate generation and severe metabolic stress.
Albumin also matters. As albumin is a major unmeasured anion, low albumin can make the apparent anion gap look falsely normal. For this reason many clinicians consider an albumin-corrected anion gap when interpreting results. A common approach is to adjust the observed value upward when albumin is low, allowing a more accurate corrected value and reducing the chance of missing clinically important acidosis.
As an example, a patient with low albumin may appear to have only a modest gap elevation, but the albumin-corrected anion gap may reveal a more significant acid burden. This matters especially in poisoned or critically ill patients, where the gap is being used as part of broader lab interpretation and not in isolation.
Common test results in isoniazid overdose
In suspected isoniazid overdose, the lab profile usually includes evidence of significant metabolic stress. An arterial blood gas may show acidic blood with decreased bicarbonate and compensatory respiratory changes. The electrolytes often demonstrate a decreased bicarbonate level and an elevated anion gap. Serum lactate may be raised because seizure activity and tissue hypoperfusion can worsen acid production.
The typical pattern is anion gap metabolic acidosis, which can appear rapidly after toxin exposure. This pattern does not prove isoniazid as the cause, but in the right clinical setting it strongly supports toxicologic evaluation. The combination of seizures, depressed mental status, and metabolic acidosis should warrant immediate attention to airway, breathing, circulation, and antidotal therapy.
Some patients may also have nonspecific abnormalities such as hyperglycemia from stress, mixed acid-base disorders, or transient respiratory alkalosis early in the course. Because these findings may change over time, repeating the arterial blood gas and electrolyte panel can aid track response to treatment and identify worsening acid-base status.
In many cases, the lab pattern is most useful when combined with bedside findings. The anion gap calculator can quickly confirm that a metabolic acidosis is present, while the overall clinical picture determines how aggressively to pursue toxicology consultation and emergency treatment.
Differential diagnosis of high anion gap acidosis
When the anion gap is raised, clinicians often consider MUDPILES, a classic mnemonic for frequent causes of high anion gap acidosis. Although this mnemonic is not exhaustive, it remains helpful in differential diagnosis during acute evaluation. The list helps organize the search for toxic alcohols, salicylates, kidney dysfunction, and other causes of metabolic acidosis.
Renal failure can lead to retention of organic acids and reduced acid clearance. Toxic alcohols such as methanol and ethylene glycol can produce profound acidosis and neurologic symptoms. Salicylates may create a mixed acid-base pattern with respiratory alkalosis and metabolic acidosis. All of these can look similar to poisoning syndromes at first glance.
In practice, the anion gap is only one part of the diagnostic workup. Because multiple toxins can present with overlapping signs, a clinician should read the gap along with history, physical findings, serum chemistries, osmolar gap when appropriate, and toxicology testing. A high anion gap in a patient with seizures and suspected ingestion should keep isoniazid toxicity high on the list while still considering alternative causes of poisoning.
The MUDPILES framework can be adapted to modern clinical practice, but the core principle remains the same: a high gap is a clue, not a final answer. It should trigger a broader search for the cause of the metabolic acidosis and guide the pace of emergency management.
Immediate management of possible isoniazid toxicity
Care of presumed isoniazid toxicity is critical. The key antidotal treatment is pyridoxine, also called the pyridoxine antidote. Pyridoxine replaces the vitamin depleted by isoniazid and helps prevent seizures and reverse the toxic mechanism. When the ingestion amount is known, dosing can be determined by the suspected amount of isoniazid taken; when it is unknown, clinicians may use empiric treatment guided by severity.
Benzodiazepines are initial therapy for active seizures or severe agitation. When seizures persist despite standard doses, toxicologic management may require repeated dosing and escalation of care. Management of seizure control is crucial because ongoing convulsions worsen lactic acidosis and can quickly destabilize the patient.
Activated charcoal may be used if the patient presents early enough and airway protection is adequate. It is not a substitute for the antidote, but it can reduce further absorption in selected cases. Because many patients with isoniazid poisoning have altered mental status or convulsions, airway safety must be assessed first.
Supportive care remains essential throughout treatment. This includes oxygen, intravenous access, cardiac monitoring, correction of hypoglycemia if present, temperature management, and treatment of shock or respiratory compromise. The overall goal is rapid stabilization while specific toxicology treatment is underway. In severe cases, emergency management may require intensive care, repeated lab checks, and ongoing reassessment of acid-base status.
When to use the calculator in clinical decision-making
The anion gap calculator should be used early in emergency evaluation when poisoning is considered, especially if the patient has seizures, unexplained coma, or evidence of acidosis. It is particularly valuable when the history is incomplete and the clinician needs a quick, objective measure of metabolic burden. In those cases, the calculator can function as a bedside diagnostic tool that aids toxicology consultation and prioritizes urgent treatment.
Use it whenever the patient has symptoms suggestive with toxin exposure and the electrolyte panel is available. A increasing gap, low bicarbonate, or worsening lactate signals escalating illness and may indicate that the patient needs closer monitoring or more aggressive intervention. If the patient has low albumin, calculate an albumin-corrected anion gap so the result is not underestimated.
Clinical decision-making should never rely on the anion gap alone. Instead, pair it with the arterial blood gas, lactate, medication history, observed overdose symptoms, and neurologic status. When the pattern is compatible with isoniazid poisoning, the calculator helps justify immediate antidotal therapy rather than waiting for definitive confirmation.
In short, the anion gap calculator is most useful when it alters action: it helps identify high-risk acid-base derangements, promotes recognition of high anion gap metabolic acidosis, and reinforces the need for rapid seizure treatment and pyridoxine administration.
Frequently asked queries
How do you compute the anion gap in possible isoniazid toxicity?
Apply: the anion gap formula: serum sodium minus the combined value of serum chloride and serum bicarbonate. An anion gap calculator can do this instantly, but the interpretation should always be made in the context of suspected poisoning, seizure activity, and the overall acid-base picture. If albumin is low, calculate an albumin-corrected anion gap for a better result.
Why can isoniazid overdose cause a raised anion gap metabolic acidosis?
Isoniazid overdose can cause severe metabolic acidosis because it triggers neurologic toxicity and seizures, which promote lactate production. This leads to lactic acidosis and a widened anion gap. The elevated gap reflects the buildup of unmeasured acids during systemic toxicity.
Must albumin be corrected when interpreting the anion gap?
Certainly, especially if albumin is low. Because albumin contributes to the normal anion gap, hypoalbuminemia can mask a true gap elevation. An albumin-corrected anion gap refines lab interpretation and helps avoid missing clinically significant acidosis.
What is the antidote for isoniazid toxicity?
The antidote is pyridoxine, also called the pyridoxine antidote. It should be given promptly in suspected isoniazid toxicity, especially when there are seizures, coma, or severe acidosis. Benzodiazepines may also be needed for seizure control, along with supportive care.
What other conditions can cause a high anion gap besides isoniazid poisoning?
Several conditions can produce a high anion gap, including renal failure, toxic alcohols, salicylates, ketoacidosis, and lactic acidosis from many causes. The MUDPILES framework is commonly used to organize the differential diagnosis. Because these disorders can overlap, the anion gap should be interpreted as part of a full toxicology and acid-base assessment.