What the anion gap is and why it counts
The anion gap is a useful way to read an electrolyte panel and recognize patterns in acid-base balance. It contrasts the main measured cations and anions in serum chemistry, helping clinicians detect hidden acids that do not appear directly on routine lab values. In practical terms, an elevated anion gap can be an key clue in metabolic acidosis, especially when the cause is not obvious from the first evaluation.
An anion gap calculator helps convert raw electrolyte data into an meaningful result. Rather than looking at numbers in isolation, the calculator supports faster recognition of systemic acidosis, hidden unmeasured anions, and the broader clinical significance of the lab pattern. This is particularly helpful in metabolic acidosis, where the body has a net acid load or a loss of bicarbonate.
In plain terms, the anion gap reflects the difference between measured positive and negative charges in the blood. When the gap is elevated, it often points to an anion deficit caused by acid accumulation. That makes it a useful diagnostic clue in the workup of an acid-base disorder. It is not a final diagnosis by itself, but it helps refine the differential diagnosis and guide next steps.
Using an anion gap calculator
To use an anion gap calculator, input the key electrolyte numbers from the electrolyte panel: sodium, chloride, and bicarbonate. These represent the core inputs used in the standard calculation formula. Certain calculators may also accept albumin input so they can provide an adjusted result.
The basic calculation formula is:
Anion gap = sodium − (chloride + bicarbonate)
This formula helps estimate the gap between measured cations and measured anions. A larger gap generally suggests the presence of additional acids in the blood. Because different laboratories use slightly different methods and reference range limits, the same lab values may produce a different interpretation depending on the calculator and the local lab standard.
As an example, if sodium is 140, chloride is 100, and bicarbonate is 20, the anion gap is 20. That result may be above the expected normal range and therefore raise concern for high anion gap metabolic acidosis. The calculator helps quickly clarify the interpretation, but the clinical picture still matters. Symptoms, kidney function, glucose, lactate, ketones, and medication exposure all affect the next step in the clinical evaluation.
Some tools also adjust for albumin, because low albumin can mask an elevated gap. In that case, the displayed adjusted value may be more accurate than the raw result for decision-making.
Normal, high, and low anion gap results
The normal range for the anion gap differs by lab technique, but the overall concept is the same: match the measured gap to the expected reference interval. A normal result usually suggests either one of no major accumulation of unmeasured acids or a compensating process that keeps the gap from rising. However, a normal value does not exclude all cases of metabolic acidosis.
A high anion gap generally indicates accumulation of acids or unmeasured anions. This is the classic pattern in high anion gap metabolic acidosis. Common causes include elevated lactic acid, ketone buildup, uremic acids, and certain poisonings. The value is best interpreted alongside bicarbonate and pH because it reflects a more significant metabolic derangement, not just a standalone lab abnormality.
A low anion gap is uncommon but can be clinically meaningful. It may occur when albumin is low, when positively charged proteins are present, or when there is a measurement issue. Because albumin contributes significantly to the normal anion gap, hypoalbuminemia can reduce the measured gap and conceal an acid-base problem. In other words, the raw number may understate the true burden of unmeasured anions.
When reviewing a result, consider whether the gap aligns with the overall pattern of electrolyte imbalance and the patient’s symptoms. A single number should never be interpreted without context. The key is whether the value is consistent with the suspected acid-base disorder or suggests another process entirely.
Frequent causes of high anion gap metabolic acidosis
High anion gap metabolic acidosis usually reflects accumulation of acids that decrease bicarbonate while resulting in unmeasured negative charges. The cause often becomes clearer once the clinical context and associated laboratory findings are reviewed.
- Lactic acidosis is common in states of poor tissue perfusion, severe infection, hypoxia, or other conditions that increase lactate production or reduce clearance. Ketoacidosis occurs when ketone bodies accumulate and consume bicarbonate. This includes diabetic ketoacidosis, starvation ketosis, and alcohol-related ketosis. Renal failure can reduce acid excretion and allow acid metabolites to accumulate. Related uremia is a classic cause of elevated gap acidosis. Toxins such as toxic alcohols can produce a dangerous rise in organic acids. These exposures require urgent recognition. Salicylates can cause complex acid-base patterns, including an elevated gap with respiratory effects as well.
These causes are important because they represent different forms of systemic acidosis and may require very different management. For example, lactic acidosis often points to hypoperfusion or severe illness, while ketoacidosis suggests insulin deficiency or carbohydrate deprivation. Renal failure and uremia point toward impaired acid handling, and toxic alcohols and salicylates can demand immediate antidotal or supportive treatment.
That is why the anion gap is so valuable: it does not just label the disturbance, it helps focus the differential diagnosis. The result provides a practical clue that should prompt targeted testing such as lactate, ketones, creatinine, osmolar gap assessment, and toxicology when appropriate.
How the albumin level affects the anion gap
Albumin is a key unmeasured negative ion in the blood, so variations in albumin can significantly affect anion gap interpretation. When albumin is low, the measured anion gap may seem normal even when hidden acids are present. This is why hypoalbuminemia is such an essential consideration in metabolic acidosis workups.
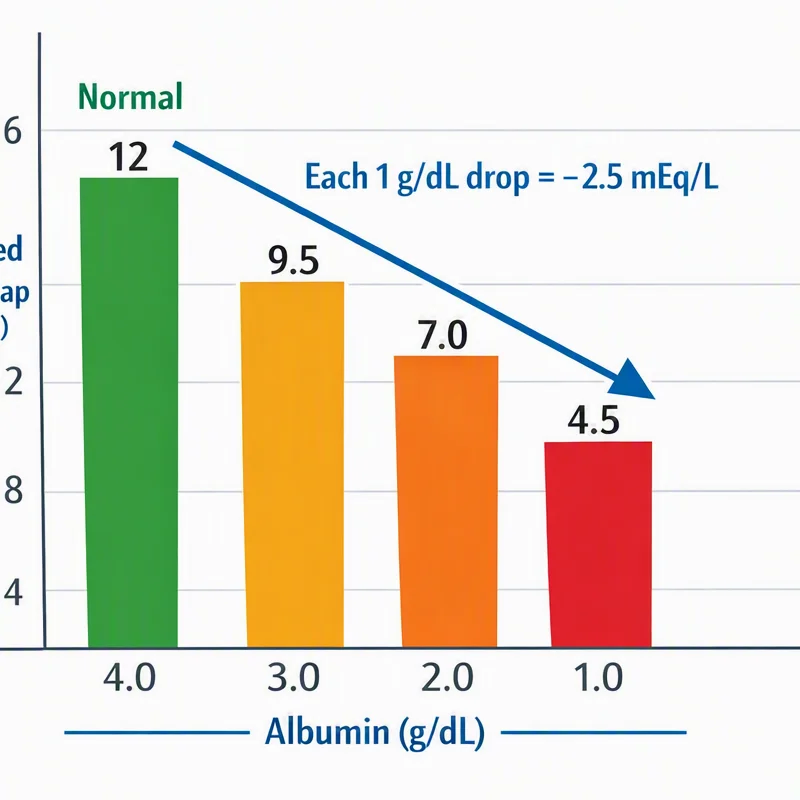
Albumin adjustment adjusts the raw result to estimate a more accurate albumin-corrected anion gap. This correction helps prevent failure to detect of a true acid load. In practical terms, the corrected anion gap is an corrected result that accounts for the reduced contribution of albumin to the gap.
A commonly used correction applies extra points to the measured gap for each decrement in albumin below normal. The exact method may differ, but the purpose is the same: increase the reliability of the result when albumin is abnormal. This becomes especially useful when evaluating a patient with metabolic acidosis and unusually normal numbers on the initial panel.
The clinical lesson is clear. If albumin is low, do not stop at the raw result. A corrected calculation may reveal that a seemingly normal gap actually reflects high anion gap metabolic acidosis. This is a critical part of accurate assessment and should be considered in any serious acid-base evaluation.
How to understand findings with the delta gap
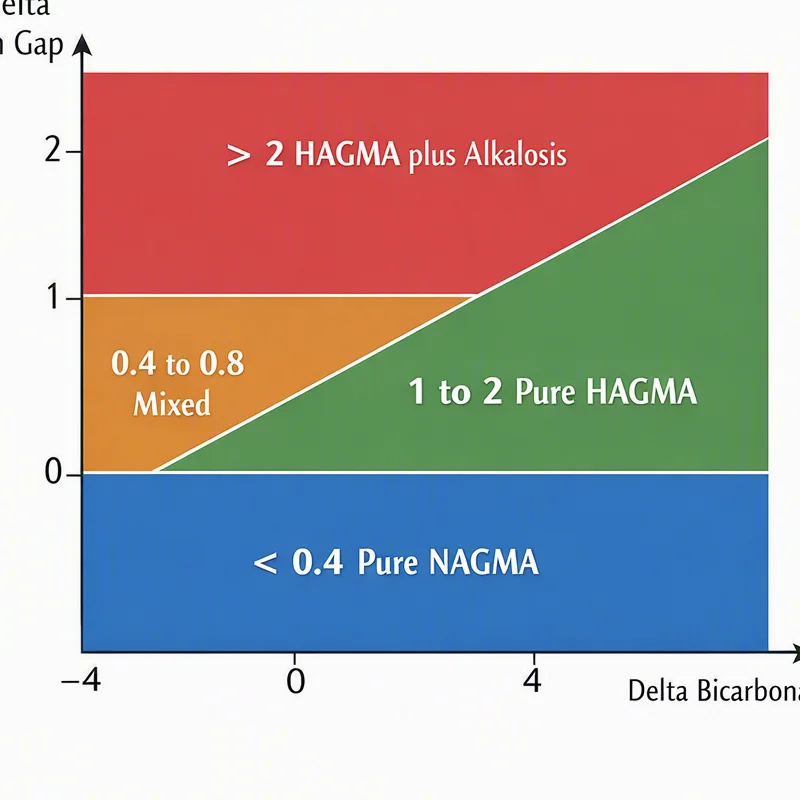
The delta gap helps determine whether the acidosis is a straightforward high-gap disorder or part of a mixed picture. It relates the rise in the anion gap to the drop in bicarbonate. The delta ratio then can reveal a possible mixed acid-base disorder.
In practice, the delta gap evaluates whether the change in the anion gap matches the expected bicarbonate deficit. If bicarbonate has fallen more than expected relative to the gap rise, there may be an additional normal-gap acidosis. If bicarbonate has not fallen sufficiently, there may be a concurrent metabolic alkalosis or chronic compensation.
The basic approach is:
- Estimate the increase in the anion gap above normal. Calculate the decrease in bicarbonate below normal. Compare the two using the delta ratio.
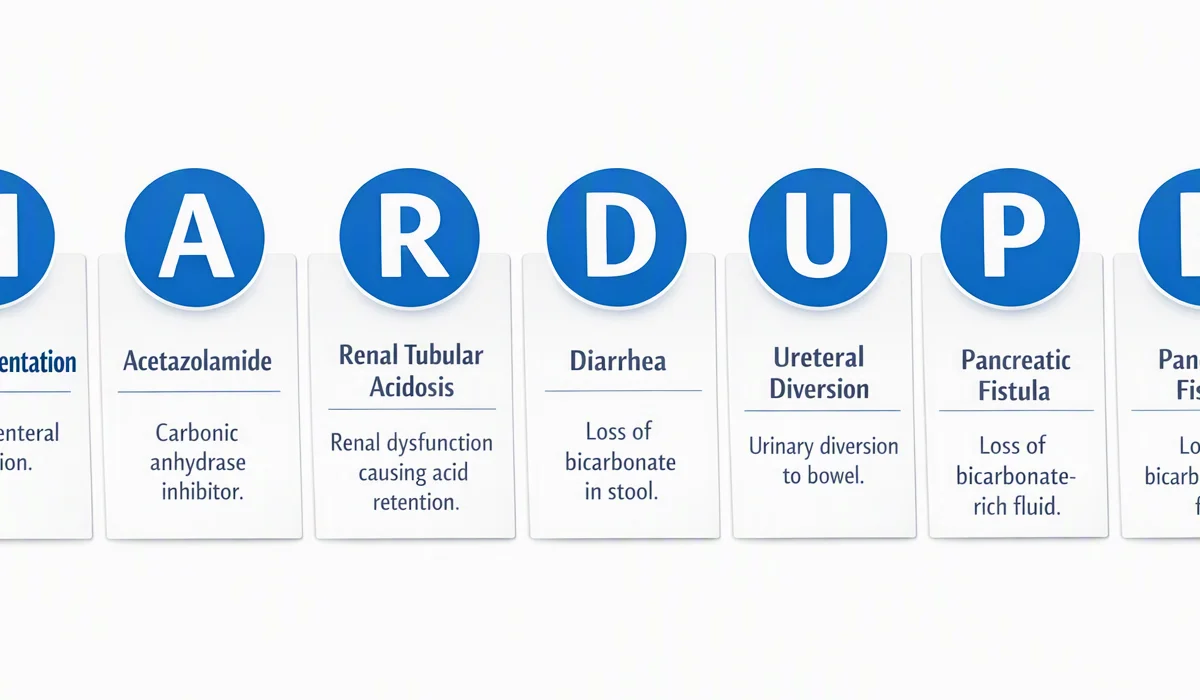
This analysis is helpful because not all patients have a isolated disorder. A person with high anion gap metabolic acidosis may also have vomiting, diarrhea, renal tubular processes, or other contributors. The delta gap gives a broader view of the acid-base picture and improves diagnostic clue quality beyond the raw anion gap alone.
For a clinician, the big question is whether the result fits the expected pattern. If it does not, the patient may have a mixed acid-base disorder that requires broader evaluation. That makes the delta analysis especially helpful in intensive or emergency settings where rapid but accurate interpretation matters.
When a reduced anion gap may be clinically important
A low anion gap is often overlooked, but it can occasionally signal an meaningful underlying problem. The first step is to rule out lab error, because testing errors or specimen problems are a typical explanation. Rechecking the test is often wise before starting a larger workup.
If the low result is verified, consider changes in proteins and electrolytes. Paraproteinemia, including multiple myeloma, can lower the gap because abnormal positively charged proteins shift the charge balance. This is one reason a low gap may be an initial clue to a plasma cell https://anion-gap-calculation.com/acid-base-disorders/nagma.html disorder.
Hypercalcemia can also contribute to a low gap, although it is uncommon. In addition, severe hypoalbuminemia can substantially reduce the measured anion gap and hide the real acid-base pattern. That is why albumin should be checked whenever the result seems unusually low.
Although a low value is not the classic pattern in metabolic acidosis, it should not be minimized. It may be the initial clue that the reported number is distorted by protein abnormalities, a measurement issue, or a broader metabolic problem. Good interpretation means confirming the result and connecting it to the patient’s overall clinical presentation.
Common questions about anion gap calculation
What is the anion gap formula?
The usual anion gap formula is sodium minus the sum of chloride and bicarbonate. Written another way, it is sodium − (chloride + bicarbonate). This calculation formula applies routine lab values from the serum chemistry panel to assess whether unmeasured anions are present.
How should you interpret a high anion gap mean in metabolic acidosis?
A high result indicates high anion gap metabolic acidosis, which usually means acids or other unmeasured anions have built up. Common causes include lactic acidosis, ketoacidosis including diabetic ketoacidosis, renal failure, uremia, toxic alcohols, and salicylates. The value is a helpful clue, not a final diagnosis.
How can you adjust the anion gap for albumin?
Albumin adjustment raises the measured result upward when hypoalbuminemia is present. Because albumin is a major unmeasured anion, low levels can hide a true acid load. The exact correction method may vary, but the goal is to derive a more accurate albumin-corrected anion gap and improve anion gap interpretation.
Can metabolic acidosis occur with a normal anion gap with metabolic acidosis?
Yes. Normal anion gap metabolic acidosis can occur when bicarbonate is lost and chloride rises to replace it, keeping the gap within the reference range. This pattern is different from high-gap states like lactic acidosis or ketoacidosis. So a normal number does not rule out metabolic acidosis; it only suggests a different mechanism.
When should a low anion gap be evaluated further?
A low result should be evaluated further if it is persistent, unexpected, or accompanied by other abnormal findings. First consider lab error, then assess albumin, calcium, and protein abnormalities. Confirmed low values may warrant evaluation for paraproteinemia and multiple myeloma, especially if the clinical picture supports it.
Using an anion gap calculator works best when it supports a larger diagnostic context rather than being considered by itself. The most effective method combines electrolytes, albumin, acid-base status, and the complete clinical evaluation. That is how a simple number becomes a practical tool for identifying and treating metabolic acidosis.