What the Anion Gap Means in Salicylate Poisoning
The anion gap is a helpful clue in the evaluation of salicylate poisoning, but it should never be treated as a single diagnosis. In toxicology, the gap helps reveal hidden acids in the blood and informs the broader acid-base balance assessment. Because aspirin exposure can produce more than one disturbance at the same time, the anion gap is often part of a broader laboratory interpretation rather than a single decisive number.
Classic aspirin toxicity often creates a mixed acid-base disorder. Early on, salicylates stimulate the respiratory center, leading to respiratory alkalosis through compensatory hyperventilation. As the poisoning advances, organic acids and impaired metabolism contribute to metabolic acidosis. The result is a pattern that can look confusing if you focus only on one value. The anion gap becomes a diagnostic clue that helps connect the serum chemistry findings to the underlying toxicology evaluation.
Salicylates interfere with cellular metabolism and can disrupt oxidative phosphorylation, which promotes the accumulation of organic acids. These metabolic derangements lower buffering capacity and may increase the anion gap. At the same time, patients may present with tachypnea, nausea, vomiting, altered mental status, or other signs of systemic toxicity. In this setting, the anion gap supports clinical correlation rather than replacing it.
A normal or only mildly elevated anion gap does not exclude salicylate poisoning, especially when the acid-base pattern is evolving.
How to Apply an Anion Gap Calculator
An anion gap calculator is a useful tool for rapid laboratory assessment during emergency assessment and poisoning workup. The basic calculation usually uses serum sodium, serum chloride, and serum bicarbonate. In its standard form, the formula is:
Anion gap = serum sodium - (serum chloride + serum bicarbonate)
Using the calculator begins with reliable serum chemistry values. First, enter the sodium concentration. Afterward, add the chloride and bicarbonate concentrations. Take away that sum from sodium to obtain the gap. This simple anion gap calculation can rapidly identify whether there is an abnormal accumulation of unmeasured anions.
In suspected salicylate poisoning, the calculator should be used as part of a wider diagnostic workflow. Look at the numerical value, but also consider the patient's symptoms, respiratory rate, mental status, and other evidence of electrolyte abnormalities. A raised number may support systemic toxicity, while a borderline result may still be clinically important if the complete picture suggests aspirin exposure.
It is also important to compare the calculated result with the laboratory’s reference range if one is provided. Different institutions may use slightly different methods or reference values, which affects laboratory interpretation. The goal is not simply to identify an abnormal number, but to use that number to guide toxicology evaluation and further testing.
Typical Lab Patterns in Aspirin Toxicity
Aspirin toxicity is known for its blended and occasionally shifting lab profile. A common early pattern is respiratory alkalosis with a low or declining bicarbonate, followed by metabolic acidosis as salicylate burden increases. This is why an arterial blood gas is especially useful. The arterial blood gas offers direct information about pH, carbon dioxide, and bicarbonate status, which helps confirm the presence of a combined acid-base disturbance.
Patients with salicylate poisoning may show a low carbon dioxide level because of hyperventilation. At the same moment, the bicarbonate may be decreased due to the metabolic component. The anion gap may increase as acids accumulate. This creates a case interpretation challenge: a patient can have near-normal pH if respiratory alkalosis and metabolic acidosis offset each other. That is one reason clinicians should not depend on pH alone when evaluating a potential toxic ingestion.
Lactate may also be raised in aspirin toxicity. However, elevated lactate does not completely explain the disturbance by itself. Salicylates can hinder energy production and drive acid generation beyond simple tissue hypoperfusion. Therefore, lactate is a helpful part of the poisoning workup, but it should be interpreted together with the anion gap, arterial blood gas, and the rest of the clinical data.
Another important pattern is that the severity of symptoms does not always match the first available lab values. Early testing may overlook the full metabolic derangement. Repeat assessment is often necessary because the toxicology evaluation can change rapidly. A patient may progress from a relatively subtle pattern to severe systemic toxicity over a short period of time.
Corrected anion gap and Albumin Adjustment
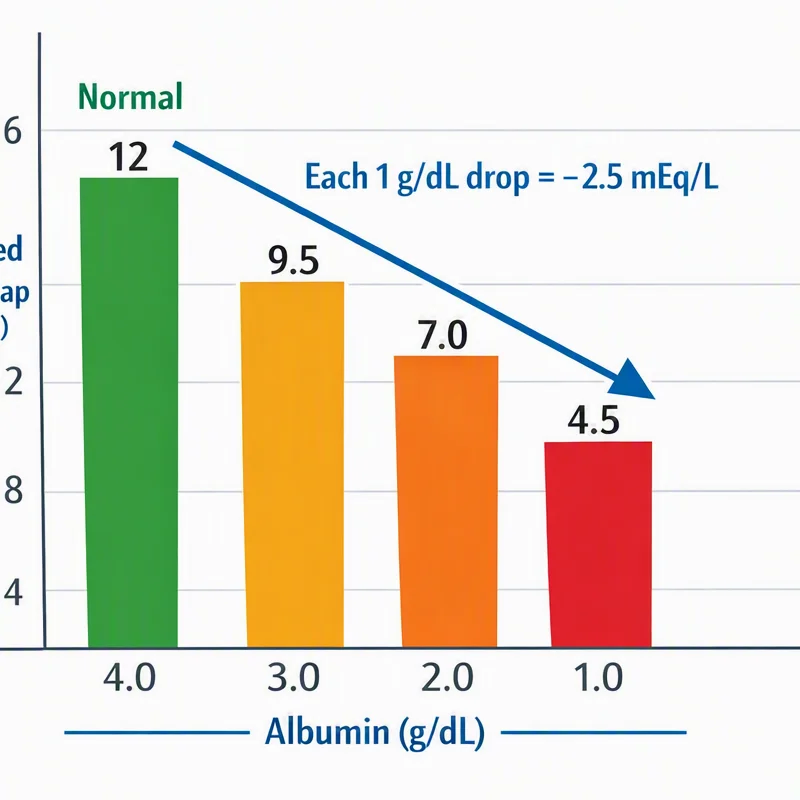
Albumin is the main undetected anion in the blood, so low albumin can make the anion gap seem deceptively unchanged. This is especially important relevant in hypoalbuminemia, where the standard gap may miss the true burden of hidden acids. For that reason, a corrected anion gap is often more precise when acid-base interpretation matters clinically.
In suspected salicylate poisoning, albumin adjustment helps avoid missing a hidden high-gap state. If albumin is low, the measured anion gap should be corrected before concluding that the serum chemistry is comforting. This step enhances diagnostic accuracy and minimizes the chance of false reassurance in a patient with possible toxic ingestion.
Corrected values are particularly useful when other findings point toward poisoning despite a near-normal number. For example, a patient may have tachypnea, nausea, ringing in the ears, and an arterial blood gas showing mixed acid-base disorder, yet the initial gap is only slightly elevated. In that setting, albumin correction can uncover a more meaningful abnormality and sharpen acid-base interpretation.
Albumin adjustment is not only about mathematics. It is about aligning the laboratory pattern to the patient's physiologic state. In clinical practice, the corrected anion gap helps synthesize acid-base balance, serum chemistry, and toxicology evaluation so the clinician can recognize systemic toxicity earlier.
When a Elevated Anion Gap Raises Concern
A elevated anion gap in the relevant clinical context should prompt concern about a significant underlying condition. In salicylate poisoning, this may reflect accumulated organic acids and altered metabolism. However, the differential diagnosis is broad, and the gap should prompt a structured evaluation rather than an assumption of a single cause.
Other common explanations include ketone production from diabetes, fasting, or alcohol-related conditions, and renal failure, where acid clearance is decreased. A toxic exposure can also produce a high gap, including salicylates, methanol, ethylene glycol, or other agents. This is why the anion gap calculator is best used as a screening and triage tool within a larger diagnostic workflow.
When the gap is raised, ask whether the pattern matches the story. Does the patient have respiratory alkalosis and metabolic acidosis together? Are there symptoms that point to aspirin exposure? Is there evidence of dehydration, reduced kidney function, or glucose abnormalities that might suggest another explanation? These questions strengthen clinical correlation and prevent incorrect labeling.
The anion gap also matters because a climbing value can signal progressive metabolic derangement. Even if the patient initially appears well, an increasing gap along with worsening symptoms may indicate advancing systemic toxicity. In that setting, repeat testing and rapid toxicology evaluation become even more critical.
Medical Follow-up Steps Once You Calculate the Gap
Once the gap is calculated the gap, the next move is to connect the result to the broader poisoning workup. If salicylate poisoning is suspected, obtain a salicylate level as soon as possible. This is important because the anion gap alone cannot quantify exposure or severity. A level helps establish the diagnosis, track trends, and guide treatment decisions.
Assess the full set of electrolytes, including sodium, chloride, bicarbonate, potassium, and any other available serum chemistry markers. Electrolyte abnormalities are common in toxic states and can affect acid-base balance. If the patient is clinically concerning, a repeat blood gas and repeat chemistry panel may be needed to follow the course.
Repeat testing is particularly helpful when the presentation is early or unclear. Salicylate concentrations may rise after the initial sample if absorption continues, especially with enteric-coated products or delayed gastric emptying. The acid-base disorder may also evolve, shifting from mixed respiratory alkalosis and metabolic acidosis toward more severe acidemia.
Reach out to poison control early when aspirin toxicity is possible. Expert guidance can help interpret the laboratory pattern, recommend follow-up testing, and support management decisions. Poison control is especially useful when the case interpretation is complicated by coexisting disease, uncertain timing, or ambiguous lab results.
At this stage, the key is integration. The anion gap calculator provides one data point, but toxicology evaluation depends on the whole picture: symptoms, lab trends, salicylate level, arterial blood gas findings, and the clinical course.
Constraints of the Anion Gap in Salicylate Poisoning
The anion gap has clear value, but it also has significant drawbacks. A normal anion gap does never exclude salicylate poisoning, especially in initial poisoning or in patients with hypoalbuminemia or mixed disorders that hide the expected result. This is one of the most important reasons not to rely on the calculator https://anion-gap-review109.huicopper.com/using-an-anion-gap-calculator-together-with-total-protein alone.
Misleading confidence can arise when providers anticipate a dramatic gap rise and overlook concerning symptoms. In early stages, respiratory alkalosis may predominate, and the metabolic component may not yet be completely evident. A patient can consequently seem sick while the gap remains normal or slightly elevated. That is why the result must be assessed with medical judgment rather than used as a test for exclusion.
Another constraint is that acid-base interpretation can be influenced by an accompanying illness. Renal failure may disturb the baseline chemistry. Ketosis can by itself increase the gap. Additional metabolic abnormalities can mask the classic pattern of aspirin toxicity. Under these circumstances, the gap remains useful, but only as part of a broader toxicology evaluation.
The main use of the anion gap is as a useful clue for diagnosis. It can reveal unseen acids, aids in spotting complex acid-base imbalance, and leads to more testing. But it is not definitive. Careful clinical judgment remains essential, especially when the presentation points to systemic toxicity but the numbers are not easy to interpret.

FAQ About Anion Gap and Salicylate Toxicity
In what way does anion gap calculator help in salicylate poisoning?
A anion gap calculator assists by promptly revealing whether there is an unclear increase in undetected acids, which can support suspicion for salicylate poisoning. It is especially useful when used with serum chemistry, an arterial blood gas, and the clinical picture. In toxicology, it serves as an initial diagnostic clue rather than a final answer.
Can salicylate poisoning occur with a normal anion gap?
Certainly. A normal anion gap can be seen in early poisoning, in mixed acid-base disorder, or when reduced albumin masks the problem. That is why a normal finding should not create false reassurance. If the medical history or symptoms suggest aspirin toxicity, more testing and medical correlation are still needed.
Why do patients with aspirin toxicity often have both respiratory alkalosis and metabolic acidosis?
Aspirin stimulate breathing, leading to respiratory alkalosis, while also impairing metabolism and generating organic acids, which causes metabolic acidosis. This combination creates a mixed acid-base disorder that can be seen on the arterial blood gas and in the anion gap. The pattern is a hallmark of toxicology evaluation for salicylate exposure.
Should the anion gap be corrected for albumin in suspected poisoning?
Absolutely, especially if albumin is low. Albumin contributes to the unmeasured anions in blood, so hypoalbuminemia can hide a meaningful gap elevation. A corrected anion gap improves acid-base interpretation and reduces the chance of missing toxic ingestion.
What labs should be checked after finding a high anion gap in suspected salicylate toxicity?
Check a salicylate level, complete electrolytes, bicarbonate, kidney function, lactate, and an arterial blood gas. Follow-up testing may be needed because the pattern can change over time. If the case is concerning, contact poison control and continue the poisoning workup with careful clinical judgment.