What’s the Anion Gap?
The anion gap is a basic but valuable value derived from routine electrolytes on a serum chemistry panel. It helps clinicians identify hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
The classic anion gap formula relates positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can indicate conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A considered interpretation of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
Why Corrected Anion Gap Counts
The usual anion gap is helpful, but it can be deceptive when albumin is reduced. Since serum albumin contains a large amount of negative electrical charge in the blood, hypoalbuminemia can reduce the measured gap even when important acids are present. That is why the corrected anion gap is important: it calibrates the number so the clinician can better judge acid-base balance.
Without albumin adjustment, a patient with substantial metabolic acidosis may look to have a comforting result. That is especially important in hospitalized or critically ill patients, where albumin may decline because of inflammation, poor nutrition, fluid shifts, or illness severity. In these settings, the corrected value strengthens diagnostic interpretation and enables more accurate decisions.
The corrected result is not meant to substitute for clinical judgment. Instead, it supplies context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still conceal a true acid load. That is why correction is often a better reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Operates
The Anion Gap Calculator simplifies the anion gap calculation so clinicians and trainees can quickly calculate the gap from everyday blood chemistry. Most calculators use a clear calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its common form, the calculation is:
anion gap = sodium - (chloride + bicarbonate)Some versions also add potassium, which somewhat changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are used in practice, but the sodium-based formula is the most common. The calculator does not diagnose disease by itself; it is a diagnostic aid that helps read the broader pattern of blood chemistry. When paired with the patient’s presenting features, pH, lactate, ketones, kidney function, and medication history, it becomes part of a full clinical interpretation.
Because the anion gap shows the difference between measured cations and measured anions, it indirectly suggests the presence of unmeasured anions. That is why it is so helpful in detecting metabolic problems that might otherwise be undetected on a standard serum chemistry panel.
Adjusting the Anion Gap for Albumin
The corrected anion gap accounts for the effect of blood albumin. Since albumin is a key negatively charged protein, decreased levels can make the gap seem falsely low or within range. The albumin correction updates the number upward when albumin is below the usual normal range.
A standard correction approach adds a fixed amount for each gram per deciliter that albumin is below normal. Various institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for adjustment. This is the practical heart of anion gap adjustment.
Why does this matter? Because low albumin can mask a true acidotic state. A patient may have a standard anion gap that looks normal, yet the corrected value reveals a clinically important elevation. That difference can change the workup, the urgency of treatment, and the interpretation of the overall acid-base balance.
Understanding the corrected result is particularly important when comparing values against a lab’s normal range. A “normal” uncorrected number may no longer be normal after adjusting for albumin. For this reason, the corrected calculation is often a more reliable reflection of the patient’s true clinical meaning than the raw value alone.
Common Causes of an Elevated Anion Gap
An elevated gap usually points to accumulation of acidic substances or uncounted anions. The leading contributors include elevated lactate, ketotic acidosis, renal failure, and specific toxic ingestions. These states can each disturb acid-base balance and show a clear elevated anion gap pattern.
Lactic acidosis can arise when tissues are underperfused or struggling metabolically, leading to excess lactate production. Ketotic acidosis arises when ketone bodies build up, often in diabetes, alcohol-related illness, or prolonged fasting. Renal failure can increase the gap because the kidneys are unable to clear acids effectively.
Toxic alcohols are another important cause of raised values. Ingestions involving methanol, ethylene glycol, and related compounds can produce serious acid-base derangements that may be life-threatening. Salicylate drugs can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
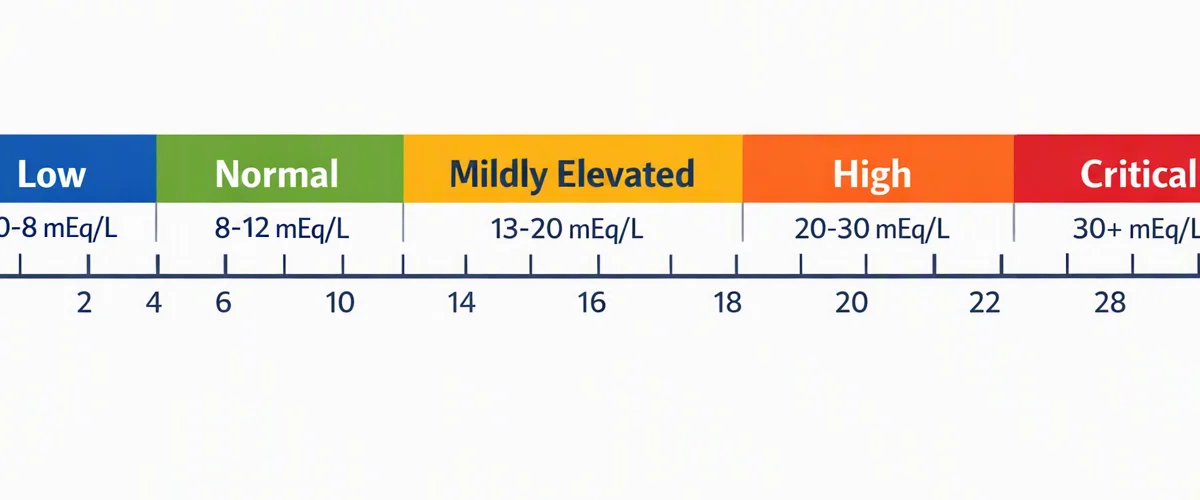
Because these disorders can overlap, the anion gap should be viewed as one piece of the puzzle. It supports clinical evaluation, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it guides the next action in the diagnostic process.
How to Interpret Low or Normal Anion Gap Results
A decreased anion gap is not as common than an elevated one, but it can still matter. Before assuming disease, the first question is whether the result is genuine. Testing error is one of the most frequent explanations, so repeating the sample is often the first step if the result is unanticipated.
A regular anion gap does not always mean there is no acid-base disorder. If the patient has hypoalbuminemia, the true gap may be missed until an albumin correction is applied. That is why the corrected value can be more revealing than the initial number when evaluating metabolic acidosis.
Another important cause of a reduced or unexpectedly normal result is paraproteinemia. Abnormal proteins can change the blood chemistry pattern and affect the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a clue that may prompt more workup.
When evaluating low or normal results, consider the entire clinical interpretation: albumin level, other electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach enhances diagnostic interpretation and helps prevent false reassurance.
Step-by-Step Example Calculation
This is a basic worked example with common laboratory values. Assume the patient has the following:
- sodium level: 140 blood chloride: 102 bicarbonate level: 18 blood potassium: 4.0
With the common sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)That gives an anion gap of 20. Provided that the lab’s reference range is lower than that, this may indicate a increased anion gap. Should the patient also has low blood albumin, the next step is adjusting for albumin to determine the adjusted anion gap.
Next assume the albumin is reduced. After applying the appropriate correction for anion gap, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. For this reason the Anion Gap Calculator is such a practical clinical tool: it makes easier the math while keeping the clinical meaning.
This sample calculation also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for metabolic acidosis, while the underlying cause may be lactic acidosis, ketone buildup, renal insufficiency, toxic alcohol ingestion, or aspirin-related compounds. The calculator does not identify the cause, but it assists in narrowing anion gap clinical significance the differential.
FAQs About Adjusted Anion Gap Results
How is defined a corrected anion gap and why is it used?
The corrected anion gap is the regular anion gap corrected for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value delta ratio calculation interpretation look falsely normal. The correction enhances clinical interpretation and more accurately shows the patient’s true acid-base balance.
How is calculated the anion gap with albumin correction?
Start with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then apply an albumin correction based on the measured serum albumin. The exact method may change by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What does a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.